

Everywhere All at Once
Joined April 2012
- Tweets11.5K
- Following3.8K
- Followers10.1K
- Likes98.6K



Don't let the ACGME do what it does best- ruin residency training!
doximity.com/newsfeed/927d2d…

Joshua retweeted

I created LearnCoronary (learncoronary.com), an interactive tool designed to help general cardiology fellows and other early-career learners better understand coronary angiography and the spatial relationships between different angiographic views.
#cardiotwitter @OpenAI
Joshua retweeted

An updated look at average physician compensation and workload
This visualization includes 89 (sub)specialties with adequate data (compared to 53 when I last posted in March). Source: @MaritHealth's crowdsourced dataset on specialties with at least 60 respondents today (contribute yours: marithealth.com)

Joshua retweeted
Components of physician task load, by specialty
Harry E et al. Jt Comm J Qual Patient Saf. 2021
sciencedirect.com/science/ar…

Joshua retweeted
Physician compensation versus physician task load (mental demand, physical demand, time demand, and effort required; correlates with burnout per Liz Harry et al. 2021) by specialty


Joshua retweeted

Thanks to @absteward for finding the most recent oral vs. IV trial for cUTI, comparing oral transitional fosfomycin to IV carbapenem. It worked, in direct contradiction to IDSA shmidelines. Updated Oral tables for Osteo, Bacteremia, IE, cIAI, cUTI, and master tables here. (1/2)


Joshua retweeted
As an editor or reviewer looking at technical medical/scientific writing, I’m personally okay with undisclosed AI writing. What matters is the authors take responsibility for the content, and it’s well written. This journal (JACC) no longer requires disclosure, a departure from ICMJE guidance. jacc.org/doi/10.1016/j.jacc.…

Joshua retweeted

There will be zero academic papers on what was lost by forcibly removing family docs from hospitals across the country and replacing them with hospitalists.

This is terrible, I'm so sorry man. Elderly care really requires doctors who are invested in the patient and know them well. I feel awful having to have these sorts of discussions with family in ICU. I wish we could bring back the old model of family doctor following the patient in the hospital. A few patients that I have had whose primary doctor did come visit, everything was so much smoother. We just chat, and they doc conveys things to the family that may take ten times longer and more painful for them. Just had one who peacefully passed away surrounded by family only because the primary doctor showed up and told them this is futile.
I'm an Emergency Physician, and I would say the best person is likely a really good, senior ER nurse! That would be my go-to on an airplane! :)

Also, please donate to help animals!!!
xitter.cf/reverendofdoubt/status…

I just donated to @humaneworldorg to help animals (and you can too!): secure.humaneworld.org/page/…

Joshua retweeted

Great talk on AI for emergency physicians!


Excited for #ACEP26 this week, and the opportunity to speak on #ECG interpretation, #AI tools like @PMcardioApp, and the paradigm shift from #STEMI to #OcclusionMI.
@ACEPNation

Joshua retweeted
Queen of Hearts’ FDA approval was the #1 most-read story in September on TCTMD, one of the leading interventional cardiology resources!


Joshua retweeted
🚑 Queen of Hearts is now available directly with corpuls ECG devices.
Our new partnership brings fast AI analysis for STEMI & STEMI-equivalent patterns to EMS crews, while connecting them directly with hospitals using @PMcardioApp for care coordination & STEMI activation!

Joshua retweeted
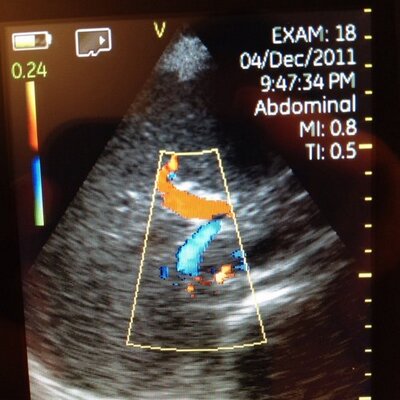
The concept that thyroid storm is an indication for beta-blockers is a widespread myth.
Indiscriminate use of beta-blockers in thyroid storm can actually kill people.
I half-heartedly tried submitting an article about this to two journals (@JHospMedicine, @CritCareExplore). JHM thought that thyroid storm isn't common enough to warrant publication in @TWDFNR. CCE never replied to my email.
So I posted it as a blog (below). A lot of smart people read it and nobody found any errors in it, which makes me pretty confident that it's a valid article.
The myth of beta-blocking everyone with thyroid storm will probably persist for a long time in the conventional medical literature. Most people who write articles about thyroid storm don't practice critical care cardiology, so my guess is that this dogma will persist for decades.

Fresh Blog: Mythbusting the use of beta-blockers for sinus tachycardia in thyroid storm
This is one of the most dangerous & pervasive myths currently in circulation about acute care
Beta-blockers commonly precipitate cardiogenic shock or even arrest in these patients..(#1/2)


I just donated to @humaneworldorg to help animals (and you can too!): secure.humaneworld.org/page/…