

Professor of Exercise Medicine with research and professional interests in exercise as medicine and S&C for athlete performance.
Perth, Western Australia
Joined September 2011
- Tweets2.1K
- Following345
- Followers11.7K
- Likes1.3K





Pinned Tweet
I’m pleased to announce the release of my new book, MyExerciseMedicine for Cancer.
This book is written first and foremost for people with cancer, survivors, and their families. I explain—in clear, accessible language—how exercise functions as a medical treatment and how it can be safely and effectively applied adjunct to surgery, chemotherapy, immunotherapy, hormone, targeted, theranostic, and radiation therapy, as well as throughout long-term recovery.
The content draws on more than 40 years of research and clinical practice in exercise medicine, including over two decades devoted specifically to exercise oncology. While the book is designed to empower patients and families with practical, trustworthy guidance, it is also highly relevant for clinicians seeking to integrate evidence-based exercise prescription into standard oncology care.
Key areas covered include:
• How exercise influences tumor biology and immune function
• Enhancing effectiveness of chemotherapy, immunotherapy, and radiation therapy
• Reducing treatment toxicity and improving tolerance
• Individualizing exercise prescription to different cancer types and stages and comorbidities
• Practical guidance to begin, progress, and maintain exercise safely and systematically
My aim is to provide a resource that supports informed decision-making, improves outcomes, and strengthens the role of exercise oncology as a core component of cancer treatment.
Amazon links:
Kindle eBook: amazon.com/MyExerciseMedicin…
Paperback: amazon.com/MyExerciseMedicin…
Hardcover: amazon.com/MyExerciseMedicin…
Thank you to the many patients, clinicians, and researchers who have contributed to this field. I hope my book proves useful for anyone seeking to apply exercise medicine to cancer treatment and survivorship.
Special thanks to @EdithCowanUni for supporting my work over the past 22 years.

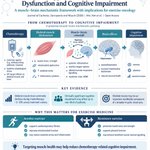
Could protecting muscle health during chemotherapy also help protect memory and thinking?
Our latest review, published in the Journal of Cachexia, Sarcopenia and Muscle, examines the potential connections between chemotherapy-induced skeletal muscle dysfunction and cognitive impairment, and what these mean for exercise oncology.
Chemotherapy can impair mitochondrial function in skeletal muscle, increasing oxidative stress and systemic inflammation. These disturbances may also contribute to inflammation and mitochondrial dysfunction in the brain, affecting neuronal health and cognitive function. Skeletal muscle may therefore be an important part of the explanation for cognitive difficulties associated with chemotherapy.
Drawing together clinical and preclinical evidence, we explore how exercise may influence this muscle–brain connection through improved mitochondrial function, reduced oxidative stress and inflammation, and changes in exercise-responsive signaling, including pathways involving irisin and brain-derived neurotrophic factor (BDNF). Importantly, these are interconnected mechanisms, not effects attributable to a single myokine.
The implication for exercise oncology is to look beyond muscle mass alone. Aerobic exercise targeting cardiorespiratory fitness and mitochondrial health, alongside resistance exercise preserving muscle mass and strength, offers a complementary approach. Further research is needed to establish how these adaptations contribute to cognitive outcomes and how best to prescribe exercise for this purpose.
Congratulations to joint first authors SoYoung Ahn and Jin-Soo Kim, and thank you to our co-authors Daniel Galvao, Dennis Taaffe, Dong Hyun Yoon, Carolyn McIntyre, Christelle Schofield, Yoon Jung Chang, Jihee Min, and Wook Song.
This work brings together our @EMRI_ECU at @EdithCowanUni and collaborators at Seoul National University and the National Cancer Center, Republic of Korea.
Read the full open-access review: onlinelibrary.wiley.com/doi/…
#ExerciseOncology #ExerciseMedicine #CancerResearch #BrainHealth
🤖 Made with AI

I have just posted my latest SubStack article: tinyurl.com/3h8c8xva
In the first two articles in this series, I reviewed the evidence that exercise can influence cancer biology, progression and survival, and then examined what CHALLENGE, ECHO and INTERVAL-GAP4 actually tell us.
We now have something the field has pursued for years: a randomized controlled trial demonstrating that structured exercise can improve disease-free and overall survival.
CHALLENGE is a landmark result. But the clinical implication is not that every person with cancer should now be prescribed the CHALLENGE protocol, nor that a generic recommendation such as 150 minutes of moderate exercise is appropriate exercise medicine for every patient. Cancer, its treatments and the resulting physiological consequences are highly heterogeneous. A patient losing muscle rapidly during treatment requires a very different exercise prescription from someone developing cardiotoxicity, osteoporosis, metabolic dysfunction or neuropathy. We also cannot assume that an exercise dose effective in healthy populations will produce the same adaptation in patients exposed to cancer therapies.
The next phase of exercise oncology research therefore needs to move beyond simply asking whether exercise works. We need to determine which exercise mode, dose, timing and duration best treats the dominant physiological problems in each patient, while also investigating whether precisely prescribed exercise can enhance the effectiveness of radiotherapy, systemic therapy and immunotherapy.
At the same time, access to exercise oncology should be expanded now because the benefits for treatment side effects, physical function, fitness and quality of life are already well established.
In this article I explore what I believe the research field needs to do next.
#ExerciseOncology #ExerciseMedicine #CancerResearch #CancerCare #PrecisionMedicine
🤖 Made with AI

I had the great pleasure of being on Dr. Geo Espinosa's Podcast and you can listen to it here: dr-geo-prostate-podcast.capt…
@drgeoespinosa02

Pain is one of the most difficult symptoms experienced by people with cancer — but exercise medicine can be part of the analgesic strategy.
Correctly prescribed exercise activates endogenous pain-control systems, including endorphins, endocannabinoids, descending pain modulation, improved circulation, reduced inflammatory tone, and myokine release from skeletal muscle.
This is not simply about distraction or general wellbeing. It is a measurable biological response.
In my latest Substack article, I discuss how exercise-induced analgesia can be used clinically during and after cancer treatment, including how exercise of non-painful regions can reduce pain sensitivity and support rehabilitation of an affected site.
Read the article here: profrobnewton.substack.com/p…
My book, MyExerciseMedicine for Cancer, is available here: amazon.com/dp/1764297512/
#ExerciseOncology #ExerciseMedicine #CancerPain #CancerRehabilitation #CancerCare #PainManagement #ExerciseInducedAnalgesia #MyExerciseMedicine
🤖 Made with AI

Thrilled to share some news! 🎉🎉 I'll be speaking at Integrative & Personalised Medicine Congress 2026 on Jun 18 - 20, 2026. I hope to see you there! #ipmcongress - via #Whova Event Platform
ipmcongress.com/

It is with pleasure that we share with you that our Graduate Certificate and Master of Exercise Science (Strength and Conditioning) programs will be Australian Government Commonwealth supported for students commencing in Semester 2, 2026. For more details please click on the links.
Graduate Certificate - ecu.edu.au/degrees/courses/g…
Masters - ecu.edu.au/degrees/courses/m…
If you are interested in enrolling and have any questions, please email the Course Coordinator, Dr Chris Latella - [email protected]
@Doc_Haff
🤖 Made with AI

Aerobic exercise in cancer care is not simply “try to walk more”
It is a prescribed physiological stimulus.
In the latest article in my Substack series, Exercise as Medicine in Oncology, I examine how aerobic exercise should be prescribed for people living with and beyond cancer.
The key issue is dosage.
Vague advice such as “go for a walk” or “stay active” can lead to both underdosing and overdosing. Too little stimulus may fail to improve aerobic capacity, fatigue, metabolic control, or treatment tolerance. Too much volume or intensity may exceed recovery capacity, worsen symptoms, or compromise muscle preservation in vulnerable patients.
In this article, I discuss:
• MICT
• interval training
• HIIT
• aerobic circuit training
• HIRT as a cardiorespiratory stimulus
• heart-rate reserve and RPE
• autoregulation during treatment
• when aerobic exercise should be modified, reduced, or temporarily avoided
• how to coordinate aerobic and resistance training
Aerobic exercise is powerful medicine, but only when the mode, intensity, duration, frequency, progression, and timing are prescribed with clinical intent.
This article draws from the framework in my book, MyExerciseMedicine for Cancer. amazon.com/dp/1764297512/
Read the article here: open.substack.com/pub/profro…
#Cancer #Oncology #ExerciseMedicine #ExerciseOncology #CancerRehabilitation #CardioOncology

Aerobic exercise is not background “cardio” in cancer care.
It is a therapeutic intervention.
In the latest article in my Substack series, Exercise as Medicine in Oncology, I examine why aerobic exercise is an essential modality in exercise oncology.
Aerobic training improves the integrated function of the heart, lungs, blood vessels, blood, and skeletal muscle mitochondria. That matters because cancer and its treatments can impair oxygen delivery, vascular function, mitochondrial efficiency, metabolic control, immune regulation, and cardiovascular health.
In this article, I discuss:
• why cardiorespiratory fitness is a powerful clinical marker
• how aerobic exercise reduces cardiovascular disease risk in cancer populations
• how aerobic training influences tumour perfusion, oxygenation, and treatment delivery
• why mitochondria matter for fatigue, oxidative stress, and possibly cognitive function
• how aerobic exercise supports immune mobilisation and inflammatory regulation
• why MICT, interval training, HIIT, aerobic circuits, and HIRT each have distinct roles
The key point is simple:
Aerobic exercise must be prescribed, not generalised.
The question is not whether a patient should “do cardio.”
The question is what aerobic stimulus is required, how it should be delivered, and how it should be adjusted to treatment, symptoms, and clinical goals.
This article draws on the framework developed in my book, MyExerciseMedicine for Cancer.
Read the article here: open.substack.com/pub/profro…
Book: amazon.com/dp/1764297512/
#Cancer #Oncology #ExerciseMedicine #ExerciseOncology #CancerRehabilitation #CardioOncology

I just signed the Axe the Tax on Health petition. Join me in calling for exercise physiology to be exempt from GST. It is a ridiculous situation in Australia where patients have to pay tax for exercise physiology services when this is not levied on physiotherapy, dietetics or psychology care.
Sign and share today.
#AxeTheTaxOnHealth gst.good.do/axethetax/axe-th…
@ESSA_NEWS

Rob Newton retweeted

We were delighted to host the Balanced MP Event at NSW Parliament!
MPs put their balance and strength to the test against Olympic Champion Duncan Armstrong.
This event highlighted the vital role of Accredited Exercise Physiologists in preventive health and mental wellbeing.
Resistance training in cancer care is not just about doing weights. It is about prescription. In practice, this is where many exercise recommendations in oncology still fall short.
Patients are often told to “do some strength training” or “use resistance bands.”
But resistance training only functions as medicine when the dose is defined:
* how hard
* how many repetitions
* how many sets
* how often
* how it progresses
* how it is adjusted around surgery, chemotherapy, fatigue, anaemia, neuropathy, bone fragility, or lymphoedema
That is what I address in the latest article in my Substack series, Exercise as Medicine in Oncology.
Part 10: Prescribing Resistance Training in Cancer Care explains:
* why 6–12 repetitions is usually the most practical therapeutic range
* why proximity to fatigue matters more than light, easy effort
* how sets, rest periods, and weekly volume determine the effect
* how to use periodisation across weeks and treatment cycles
* when advanced methods such as cluster sets or accentuated eccentric loading may be useful
* why resistance training must be programmed, not generalized
Resistance training is one of the most direct treatments we have for opposing treatment-related decline.
It preserves muscle mass, improves muscle quality, increases strength and power, supports bone integrity, and helps maintain the physiological reserve required to tolerate therapy and remain independent.
Read the latest article here:
open.substack.com/pub/profro…
#Cancer #Oncology #ExerciseMedicine #ResistanceTraining #CancerRehabilitation #ExerciseOncology

Excited to share our latest publication in the Journal of Strength and Conditioning Research:
Sex-Specific Immune Cell Mobilization and Recovery After High-Volume Glycolytic Squat Exercise
William J. Kraemer, Mastro AM, Saenz C, Freidenreich DJ, Volk BM, Gomez AL, Fragala MS, Szivak TK, Post EM, Wolf MR, Comstock BA, Häkkinen K, Newton RU, Jeff Volek.
This study examined how men and women differ in their acute immune response to a single bout of high-volume glycolytic resistance exercise.
Among the key findings:
Resistance exercise triggered a rapid and robust immune cell mobilization response.
Men showed a greater transient increase in circulating lymphocytes, particularly natural killer cells, shortly after exercise.
Women demonstrated a different recovery pattern, including increases in CD4+ cells at 60 minutes postexercise.
Both sexes showed substantial time-dependent changes in immune cell populations during early recovery.
These findings reinforce that resistance exercise is a potent immunological stimulus, while also highlighting that the magnitude and timing of the response are partly sex-specific.
Understanding these acute responses may help inform more precise exercise prescription and recovery strategies, while contributing to our broader understanding of the interaction between exercise and immune function.
DOI: 10.1519/JSC.0000000000005443
#ResistanceTraining #ExerciseImmunology #StrengthAndConditioning #SportsScience #ExerciseScience #ImmuneFunction #Research #JSCR #ExercisePhysiology
journals.lww.com/nsca-jscr/a…

Resistance training is still underused in cancer care. That needs to change.
In the latest article in my Substack series on Exercise as Medicine in Oncology, I examine why resistance training is not an optional adjunct to cancer care, but a primary treatment modality.
Resistance training is the most effective exercise intervention we have for preserving or rebuilding muscle mass, improving strength and power, supporting bone integrity, and maintaining the physical reserve required to tolerate cancer treatment and preserve independence.
It also matters biologically.
Skeletal muscle is not simply tissue for movement. It is a major endocrine, metabolic, immune, and neuroprotective organ. When it is lost, patients lose far more than strength.
In this article, I discuss:
why resistance training is foundational in exercise oncology
the endocrine and immune role of skeletal muscle
the relevance of myokines to cancer biology
why general activity is not a substitute for resistance training
why muscle preservation matters for treatment tolerance, physical function, and long-term outcomes
This article is based on the framework developed in my book, MyExerciseMedicine for Cancer, which brings together the scientific and clinical foundations of exercise oncology across the cancer continuum.
You can read the latest article here:
👉 profrobnewton.substack.com/p…
And the book is available here:
👉 amazon.com/dp/1764297512/
#Cancer #Oncology #ExerciseMedicine #ResistanceTraining #CancerRehabilitation #ExerciseOncology
Excited to share our latest paper, just published in the Journal of Ageing and Longevity: “The Effect of Boosting Dietary Lactobacillus and Phytochemical Rich Foods on Biomarkers of Longevity—A Phase II Randomised Placebo Controlled Trial.”
mdpi.com/2673-9259/6/2/35
In this double-blind randomised controlled trial involving 208 older men with untreated early prostate cancer on active surveillance, we found that boosting phytochemical-rich foods was associated with improved grip strength over 4 months, and that the addition of a Lactobacillus probiotic was linked to even greater improvements in grip strength, lower neutrophil-to-lymphocyte ratio, and higher testosterone at trial completion.
Grip strength is a practical and meaningful marker of health span and ageing, so these findings add to the growing interest in how diet, gut health, and targeted nutritional strategies may influence functional ageing. Importantly, the interventions were also well tolerated.
This work highlights the potential synergy between phytochemical-rich foods and probiotics, and points to the need for larger and longer studies using more definitive clinical outcomes.
Congratulations to my co-authors and collaborators on bringing this study to publication.
#Research #HealthyAgeing #Longevity #Nutrition #GutHealth #Probiotics #Phytochemicals #GripStrength #ProstateCancer #ExerciseMedicine
🤖 Made with AI

Exercise is only medicine when it is prescribed with precision.
In cancer care, telling patients to “stay active” is often not enough. The type, dose, and progression of exercise must match the clinical problem.
Walking may help reduce inactivity, but it will not adequately treat muscle loss, weakness, or low bone density. Different exercise modes have different therapeutic mechanisms.
That is why exercise prescription should be approached with the same clinical discipline as any other therapy: the right treatment, for the right patient, at the right time.
My latest SubStack article explores the principles of exercise prescription in oncology and why skeletal muscle should often be a primary therapeutic target.
open.substack.com/pub/profro…

FitMed is supporting me to deliver workshops on precision exercise oncology in London and Lisbon this June - I am hugely thankful for the support. FitMed has put two modules together, the first entirely online which students complete at their own pace. The second is a face to face practical workshop which I am very excited to be teaching.
Full details are available at FitMed Academy: fitmed.com/fma-exercise-onco…

Is it safe for people with cancer to exercise?
Or are we asking the wrong question?
The issue is not whether patients can exercise.
The issue is whether we are screening and prescribing it properly.
Cancer is a chronic disease. The same structured risk assessment we apply in other chronic conditions should apply here — with additional consideration for treatment effects, bone health, and symptom burden.
In practice, exercise safety is not determined by avoiding activity.
It is determined by:
• appropriate screening and risk stratification
• correct setting and level of supervision
• adjustment of mode, intensity, and dose
• ongoing monitoring and autoregulation
When this is done properly, nearly all patients can participate safely — including those with advanced disease.
In Part 7 of my Substack series on Exercise as Medicine in Oncology, I outline:
• how the ESSA screening framework applies in cancer
• how risk determines supervision and exercise setting
• how to use perceived exertion to guide intensity
• when exercise should be modified vs paused
Exercise safety in oncology is not about restriction.
It is about precision.
Read the article here: profrobnewton.substack.com/p…
#Cancer #Oncology #ExerciseMedicine #ExerciseOncology #ClinicalPractice
