







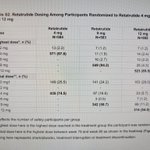


First blush thought. Reta but more diarrhea, nausea/vomiting signal looks weird, increased lipase 15-20% is 🧐🧐 worth watching. Heart rate increases up to 10BPM, 6MG arm confounded ~25% of patients never took 6mg dose. Probably viable molecule but it'll be 3 years too late.

Cell metabolism publication: cell.com/cell-metabolism/abs…

David W retweeted

If someone miraculously invented a drug that:
- successfully reversed obesity and most of its associated diseases
- improved longevity
- decreased the long term health costs
….and it was NOT covered by health insurance, ….
- then what would be the use of health insurance?
Can an oral small molecule provide renal and cardiovascular benefits just like the injectable GLP1 meds? The answer is probably so! New blog post today about Achieve 4 the CV trial that was presented at EASD.
the-incretins.beehiiv.com/p/…

David W retweeted

Managing iron-deficiency anemia is a challenge in CKD. This randomized trial in #ASNCJASN found that adding lactoferrin to oral iron improved hemoglobin and iron status more than iron alone, suggesting a potentially accessible treatment strategy. kidney.pub/CJASN11204

The cadence here is wild. Next year will be Reta launch + Tirz for Type 1 diabetes, Foundayo for Type 2, Then Elora in late 2028. Then EloraTZP in late 29/30. Brenipatide will probably be 2028. They're not slowing down at all.

Thanks to my Reddit friends for the heads up. Apparently there was a Lilly Investor call for EASD 2026, but there’s no archived audio. 😔
But look at this little beaut. Some additional details on P3 for EloraTZP.
▪️AMPLIFY studies for EloraTZP starting late 2026/early 2027 and ending in 2029.
▪️AMPLIFY-1: EloraTZP, tirzepatide alone & eloralintide alone, BMI > 35 without T2D
▪️AMPLIFY-2: EloraTZP vs. tirzepatide, with T2D
▪️AMPLIFY-3: EloraTZP, tirzepatide alone & eloralintide alone, BMI ≥ 27 to < 35 without T2D
➡️ Lilly seems to be purposefully separating the trials into different BMI categories, which should provide a clearer picture for prospective patients on likely response/trajectories. SMART. ❤️
Lilly will have to apply all lessons learned from TRIUMPH to their trial protocols, especially AMPLIFY-3. One hopes they provide adequate lower doses for de-escalation.
investor.lilly.com/static-fi…

David W retweeted

😲 The most shocking info that David (@rn_flex) highlighted in this piece was the difference in the A1C reductions between CagriSema and EloraTZP.
▪️The two amylins clearly have very different efficacy for A1C reduction. In REIMAGINE 2, Cagrilintide 2.4 mg showed a -0.8 reduction in A1C (efficacy estimand), while Elora showed reductions of -1.06 to -1.42 on its own in its T2D P2.
▪️All 5 EloraTZP arms had at least 90%% of patients hitting an A1C < 7%, and two arms had 100%, compared to 82% for CS 2.4/2.4mg.
▪️4/5 of the EloraTZP arms had 66-77% of patients reach normal glycemia (A1C < 5.7%), and the 5th (the lowest dose arm) hit 45%, while CS 2.4/2.4mg only had 20.6% achieve normal glycemia.
▪️Baseline A1C were 8.2% for REIMAGINE 2, and 8.14% for the EloraTZP P2.
The normal glycemia data for CS is pulled from their ADA presentation. I could not find it in the REIMAGINE-2 paper.
Also added the TRIUMPH-2 A1C data for retatrutide, but I should note that the baseline A1C was 7.7%.


🔥 It feels foolish to post TWO @rn_flex articles in one day, but here we are.
▪️GREAT REVIEW of the whirlwind that was Tuesday and Wednesday of EASD 2026, plus a pretty great synopsis of how wild the last 10 years have been in GLP-1s
▪️Retatrutide TRIUMPH-1 and -2 and Elora Tirz P1 & T2D P2
▪️If you want to be excited about future treatment *possibilities*, this is a great review of retatrutide and eloralintide + tirzepatide
▪️Caveat: There’s definitely still work to do in optimizing tolerability and safety, and figuring out how to report all of this back to trial readers (docs, investors, and patients)
Humor: Pretty sure there’s a dungeon and dragons/dice-based role playing game reference in there 🤦♀️, plus a classic Jurassic Park one as well 🦕.
[Yes, I’m admitting to playing a weekend or two of D&D in my foolish college years.]
the-incretins.beehiiv.com/p/…

David W retweeted
🔥 It feels foolish to post TWO @rn_flex articles in one day, but here we are.
▪️GREAT REVIEW of the whirlwind that was Tuesday and Wednesday of EASD 2026, plus a pretty great synopsis of how wild the last 10 years have been in GLP-1s
▪️Retatrutide TRIUMPH-1 and -2 and Elora Tirz P1 & T2D P2
▪️If you want to be excited about future treatment *possibilities*, this is a great review of retatrutide and eloralintide + tirzepatide
▪️Caveat: There’s definitely still work to do in optimizing tolerability and safety, and figuring out how to report all of this back to trial readers (docs, investors, and patients)
Humor: Pretty sure there’s a dungeon and dragons/dice-based role playing game reference in there 🤦♀️, plus a classic Jurassic Park one as well 🦕.
[Yes, I’m admitting to playing a weekend or two of D&D in my foolish college years.]
the-incretins.beehiiv.com/p/…
David W retweeted
Let’s look at this, shall we?
▪️The standards for inclusion only appear to require a SINGLE GLP-1 injectable SCRIPT (not a fill) prior to switch. So some people in this might not have ever taken an injectable, if they ran into insurance or cost issues.
▪️41% of those switched from Zepbound had 2.5mg as their last script before switching. Thats just the intro dose and not approved for weight loss efficacy.
▪️69% of those switching from injectable Wegovy were on 1mg or lower for their last script before switching. 1.7mg is the first dose approved for weight loss efficacy.
▪️Mean BMI change over 3 months was 1.4 and mean loss was 4kg (8.8lbs).
▪️That may be *statistically* significant, but is it that stage sort of significance patients are expecting when you say “significantly”?
▪️They don’t break out results by starting treatment AT ALL.


#PRESS: What happened when people switched from weight-loss injections to a pill?
Learn more about the findings, presented at EASD 2026, in our press release: novonordisk.com/content/nnco…

David W retweeted

Certainly its becoming less practical, and much less informative, to try to compare novel therapy to something below the best standard of care. Drop in rates of GLP-1 and the rising attrition rates in placebo confound effect sizes, make studies less interpretable and demonstrate patient need. Since the approved molecules are now abundant, should be standard of care for obesity management, and increasingly reimbursed - your point is a good one.

Finishing my lunch and didn't expect to find this incredible post from Dave Ricks.
Guess I'm not the only one to throw shade in the direction of a certain company.

Well I should have added a few more critical questions to this list
-Peer reviewed and presented at a medical meeting or published in a journal >>> pre print + press release while a meeting is going on
- For post hoc or RWE publish your methods and caveats, your sample and absolute event rates and measures - better to have it verified by independent group - real science is transparent and can be replicated.
Anyways. My latest blog post on insulin sensitivity is live. Discusses how Lilly went from GIP is probably adding something to insulin sensitivity to fully proving it in humans. Elegant iterative data over a few different trials. Good stuff.
the-incretins.beehiiv.com/p/…

David W retweeted

Hey #NephJC 👋
Checkout the VA by @DivyaveerSSNeph
This week we're looking at steroid weaning strategies in adults with podocytopathies (MCD/FSGS).
💊Steroids: easy to start but hard to stop.
#NephTwitter
nephjc.com/news/starttrial

Not designed for weight loss. Test low doses for phase 1. Still causing significant weight reductions in 11 weeks and with minimal GI side effects(same as placebo)

@rn_flex gives his read on all the new data on GIP for VK2735, enicepatide and Brenipatide. Flex says, “All hail the current and future GIP kings.” 👑😂
New info: Brenipatide has a half around 10 days and, even though it’s being targeted as a psych med, still shows double digit weight loss. 😲
the-incretins.beehiiv.com/p/…

David W retweeted

@Roche notches impressive P2 data for the GLP-1R-GIPR co-co-agonist Enicepatide #T2D #weightloss roche.com/media/releases/med…

This guy continues to just be wrong. They have the resources to do both. And yet. They won't. Same mistake as Amylin vs GIP. And if the medicare bridge has taught me anything. Patients want results & tolerance first. Convenience is usually 2nd.

LIVE: $NVO Head of R&D Martin Holst Lange says pills are the future because they are convenient for patients and do not require refrigeration.
He believes oral large-molecule drugs can offer efficacy advantages over small molecules, and Novo is exploring pills not only for obesity and diabetes but potentially also for hemophilia.
Novo is now working with the third generation of its technology for delivering large molecules orally, with each generation designed to increase the amount of active drug that reaches its target.

It also decreased composite kidney outcomes in the overall populations(HR 0.74 CI 0.58-0.93) and directionally similar with the high risk group (HR 0.79, CI 0.55-1.14) and 🔽 UACR by ~28% for both groups
AND "Effects on eGFR and UACR were consistent regardless of SGLT-2i use."