

Associate Prof @HarvardMed, MGH; Senior Lecturer @MITSloan. Systems scientist, developing simulation models for population-based health problems
Boston, MA
Joined October 2009
- Tweets2.5K
- Following486
- Followers2.2K
- Likes4.3K







Pinned Tweet
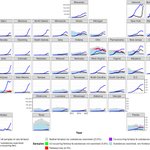
The national opioid overdose death trend in the US turned downward, and there’s been plenty of speculation about why. Our new letter in @JAMAPsych uses our SOURCE model to explain the shift
jamanetwork.com/journals/jam…

1
1
87
Had a great time speaking to a visiting group of hospital executives from China about how systems thinking and modeling can support real operational and strategic decisions, from patient flow and staffing to resource allocation and technology adoption. Loving these opportunities!

1
315
The SOURCE model, published a few years ago in @pnas, had already projected a decline driven by two forces: a steadily shrinking population at risk and a plateau in overdose mortality as fentanyl’s rapid rise stabilized.
(Original SOURCE study: pnas.org/doi/full/10.1073/pn…)

1
1
49
M.J. retweeted

Recent US #opioid overdose deaths have declined 41%, mainly due to a shrinking at-risk population and plateauing mortality rates.
Continued surveillance is needed to predict and prevent harm.
ja.ma/4p7AtEs

I recently launched the Best Paper in Health Data & Systems Science Award to recognize the strongest mentee paper from the past 2 years in our lab. Grateful for the energy and curiosity people bring to the lab! Learn more here: mj-lab.mgh.harvard.edu/wp-co…
1
56
Using 1M+ forensic lab reports, our new study traces a decade of changes in substances found w fentanyl. We show xylazine’s sharp rise past heroin, identify when/where multi-drug combinations appeared and offer a granular view of how these patterns shifted sciencedirect.com/science/ar…
56
New perspective: Hospitals face cyber threats shaped by human decisions under pressure, but collecting behavioral data is often limited. Synthetic behavioral data + simulation may offer a way to explore these patterns, though it needs careful evaluation: journals.plos.org/digitalhea…
1
50
M.J. retweeted

Our research shows that while cutting NIH funding may appear to save money in the short term, it can trigger a chain of effects that increase long-term healthcare costs and slow the development of new treatments and public health solutions. f-st.co/ADSzj5A

M.J. retweeted

Proposed cuts to NIH funding would have ripple effects on research that could hamper the US for decades theconversation.com/proposed…

Delighted to welcome Dr. Songul Cinaroglu, Associate Professor of Health Care Management at Hacettepe University in Turkey, to our lab this year as a Fulbright Visiting Scholar.
2
170
The sad irony: funders want to include community members with no grant-writing background, but their applications are so demanding that even seasoned applicants struggle
137
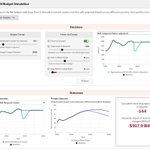
What happens when research funding gets cut (not just a little, but a lot)? Try our simulator to find out.
Our model BRIDGE quantifies the impact of NIH budget cuts in the US, built on 47 datasets (1995-2024) and projecting effects over 25 years.
mj-lab.mgh.harvard.edu/nih-b…

M.J. retweeted

Study: NIH Cuts Could Undermine Innovation, Raise Long-Term Costs ow.ly/bXHk106hbFv
M.J. retweeted

Potential effects of cuts to the @NIH
1) slow future innovations
2) shrink the future biomedical workforce
3) increased health care expenditures
4) missed opportunities for disease prevention, further increasing health care expenditures.
jamanetwork.com/journals/jam…

"Reducing NIH budget doesn’t just mean fewer grants; it means fewer trainees entering the pipeline, slower progress on treatments, more reliance on expensive late-stage care and weakened capacity for public health."
politi.co/454nFpy via @politico
jamanetwork.com/journals/jam…
92
NIH spending battle’s ripple effect politi.co/454nFpy via @politico
Full text of study: jamanetwork.com/journals/jam…

1
87
M.J. retweeted

This analysis in @statnews lays out how the proposed NIH budget cuts will actually waste more funds than they save & hurt science and medical progress
statnews.com/2025/07/28/nih-…

M.J. retweeted
NIH BUDGET CUTS: The proposed budget cuts by the White House to the NIH will have far reaching implications for public health- @NIHDirector_Jay working on budget negotiations with Congress this summer
jamanetwork.com/journals/jam…