






Mo retweeted

Come on NWBO family, or anyone of my golf followers! Let's do something good today! I've made my donation and will continue to donate until it's no longer needed.

We need your help getting Braelyn to her next DCVax-L treatment on November 6. 💜
We still need to raise $16,795 to cover her November treatment. Her airfare and lodging have graciously been covered by a private donor, so every dollar raised now can go directly toward these treatment costs.
If you can donate or simply share, we would be incredibly grateful. Help us keep fighting for Braelyn’s hope and a future. 💜
#DCvaxForBraelyn
gofund.me/a51b39a90

Mo retweeted

We need your help getting Braelyn to her next DCVax-L treatment on November 6. 💜
We still need to raise $16,795 to cover her November treatment. Her airfare and lodging have graciously been covered by a private donor, so every dollar raised now can go directly toward these treatment costs.
If you can donate or simply share, we would be incredibly grateful. Help us keep fighting for Braelyn’s hope and a future. 💜
#DCvaxForBraelyn
gofund.me/a51b39a90
🤖 Made with AI

Mo retweeted

We don't forget.
That includes you @BrettHarrison

BREAKING 🚨: How corrupt is the United States? The day after the Justice Department launched an investigation into Wall Street short sellers the largest document storage facility, TD Ameritrade Bartlett Warehouse, went up in flames. They hauled the evidence away ON FIRE in direct violation of OSHA safety requirements. 60 hedge funds were to undergo investigations for manipulative short selling. Authorities concluded that a “falling shelf” took out the entire building’s sprinkler system that was located on the roof.
⠀
The facility was a newer facility outfitted with state of the art fire prevention technology.
⠀
Hedge funds have been under heavy scrutiny from retail investors.
⠀
More specifically from the AMC and GME community after the ‘meme stock’ frenzy early last year, 2021
⠀
Hedge funds have been able to suppress the share price of both these stocks through predatorial short-selling strategies.
⠀
In a Bloomberg exclusive, Gary Gensler states 90%-95% or retail market trades do not go through the lit exchange, but rather through dark pools.
⠀
This happened on February 4th 2022. Just like everything with out government absolutely NOTHING has come from the investigation. No charges. No stop to the blatant naked short selling taking place on a daily basis robbing investors.
⠀
The primary offender of naked shorting of course is Citadel, owned by Ken Griffin. Griffin is Ron DeSantis’s MEGADONOR and #WEF member.
Mo retweeted
How many stories does it take before people take notice? NWBO and DCVax-L are making real life differences and people dismiss the science because of the stock price?? Unbelievable

$NWBO #DCVaxForBraelyn #GBM
Siobhain, Margaret’s Trial deserves support. Your campaign could also put an urgent question to government:
𝗪𝗵𝘆 𝗱𝗼𝗲𝘀 #𝗗𝗖𝗩𝗮𝘅-𝗟 𝘀𝘁𝗶𝗹𝗹 𝗮𝘄𝗮𝗶𝘁 𝗮𝗻 𝗮𝗽𝗽𝗿𝗼𝘃𝗮𝗹 𝗱𝗲𝗰𝗶𝘀𝗶𝗼𝗻?
Northwest Biotherapeutics has completed a phase III programme, published survival findings, documented a favourable safety record across thousands of doses, and developed a platform with a compelling rationale for combination treatment.
The company and the people behind that work deserve to be part of this conversation.
𝗗𝗿. 𝗔𝗹𝘁𝗼𝗻 𝗕𝗼𝘆𝗻𝘁𝗼𝗻. 𝗗𝗿. 𝗠𝗮𝗿𝗻𝗶𝘅 𝗕𝗼𝘀𝗰𝗵. 𝗣𝗿𝗼𝗳𝗲𝘀𝘀𝗼𝗿 𝗞𝗲𝘆𝗼𝘂𝗺𝗮𝗿𝘀 𝗔𝘀𝗵𝗸𝗮𝗻.
Boynton co-founded Northwest. Bosch joined in 2000 and spearheaded development of its manufacturing and quality-control processes, alongside clinical protocols and regulatory submissions.
Their work helped turn dendritic-cell biology into a personalised product that could be manufactured, transported and administered across an international clinical programme.
That translation is an achievement in itself. Every patient supplies different cells and a different tumour. The treatment must still be prepared consistently enough to test and deliver.
Here in Britain, Professor Keyoumars Ashkan, neurosurgeon at King’s College Hospital, served as the trial’s European Chief Investigator. He is a coauthor of the phase III publication, alongside UCLA’s Dr. Linda Liau, Boynton, Bosch and the international clinical team.
𝗕𝗿𝗶𝘁𝗶𝘀𝗵 𝗰𝗹𝗶𝗻𝗶𝗰𝗶𝗮𝗻𝘀 𝗮𝗻𝗱 𝗽𝗮𝘁𝗶𝗲𝗻𝘁𝘀 𝗵𝗲𝗹𝗽𝗲𝗱 𝗴𝗲𝗻𝗲𝗿𝗮𝘁𝗲 𝘁𝗵𝗶𝘀 𝗲𝘃𝗶𝗱𝗲𝗻𝗰𝗲.
kch.nhs.uk/news/final-result…
The scientific argument begins with a basic requirement: the immune system needs effective instruction about what to attack.
Dendritic cells present tumour antigens, provide activating signals and shape the responding T cells. Tumours can interfere with that process.
DCVax-L makes preparation of those instructing cells part of treatment. The patient’s own dendritic cells are prepared outside the tumour environment and loaded with material from the patient’s own tumour.
Whole-tumour material supplies a broad range of potential targets through the patient’s own presentation machinery. That matters in glioblastoma, where different cancer cells can carry different targets.
𝗣𝗲𝗿𝘀𝗼𝗻𝗮𝗹𝗶𝘀𝗮𝘁𝗶𝗼𝗻 𝗶𝗻𝗰𝗹𝘂𝗱𝗲𝘀 𝘁𝗵𝗲 𝗰𝗲𝗹𝗹 𝗱𝗼𝗶𝗻𝗴 𝘁𝗵𝗲 𝘁𝗲𝗮𝗰𝗵𝗶𝗻𝗴.
The work discussed by Lisa Butterfield and Pawel Kalinski makes preparation even more consequential. Cells can pass routine checks while retaining signalling or metabolic defects. A mature appearance does not establish effective immune instruction.
Starting-cell quality, culture conditions and maturation signals all shape function. IL-12p70 is an important part of type-1 instruction, but no single marker establishes the entire cell’s performance.
This is why Bosch’s manufacturing work matters biologically. Preparing the cell creates an opportunity to assess and improve the instruction before treatment reaches the patient.
𝗧𝗵𝗲𝗻 𝘁𝗵𝗲 𝘀𝗲𝗾𝘂𝗲𝗻𝗰𝗲 𝗺𝗮𝘁𝘁𝗲𝗿𝘀.
Pembrolizumab releases inhibition on T cells. Dendritic-cell vaccination can help generate the tumour-directed response that checkpoint treatment is intended to support.
UCLA’s EANO 2026 report examined its related ATL-DC vaccine with poly-ICLC and pembrolizumab in recurrent glioblastoma.
Among the analysed IDH-wildtype patients:
𝗩𝗮𝗰𝗰𝗶𝗻𝗲 𝗳𝗼𝗹𝗹𝗼𝘄𝗲𝗱 𝗯𝘆 𝗽𝗲𝗺𝗯𝗿𝗼𝗹𝗶𝘇𝘂𝗺𝗮𝗯: 𝟱𝟱𝟱 𝗱𝗮𝘆𝘀 𝗺𝗲𝗱𝗶𝗮𝗻 𝘀𝘂𝗿𝘃𝗶𝘃𝗮𝗹.
𝗣𝗲𝗺𝗯𝗿𝗼𝗹𝗶𝘇𝘂𝗺𝗮𝗯 𝗯𝗲𝗳𝗼𝗿𝗲 𝘀𝘂𝗿𝗴𝗲𝗿𝘆 𝗮𝗻𝗱 𝗮𝗹𝗼𝗻𝗴𝘀𝗶𝗱𝗲 𝘃𝗮𝗰𝗰𝗶𝗻𝗮𝘁𝗶𝗼𝗻: 𝟮𝟳𝟭 𝗱𝗮𝘆𝘀.
The groups contained 16 and 19 patients. This small, amended trial also found greater T-cell infiltration and interferon/granzyme-B signals in the vaccine-first group. Earlier/concurrent treatment was associated with chronic inflammatory responses.
Elevated interferon responses before treatment tracked with shorter survival.
The distinction matters: timing, location and the state of the immune system can change what an immune signal accomplishes.
𝗘𝘀𝘁𝗮𝗯𝗹𝗶𝘀𝗵 𝘁𝗵𝗲 𝗿𝗲𝘀𝗽𝗼𝗻𝘀𝗲. 𝗧𝗵𝗲𝗻 𝗵𝗲𝗹𝗽 𝗶𝘁 𝘄𝗼𝗿𝗸.
EANO 2026, abstract MO03.4.A:
eano.eu/eano2026/programme/
Trial:
clinicaltrials.gov/study/NCT…
The vaccine course allowed only three doses, two weeks apart. Pembrolizumab continued; vaccination ended within weeks.
A short course was followed by a survival difference measured months later.
Immune memory, recruitment of the patient’s own dendritic cells, reciprocal signalling and recognition of additional tumour targets offer biological routes to a response that outlasts the injected cells. Their contribution requires measurement, but the possibility is central to the strategy.
And 555 days is the median. Longer follow-up is needed to reveal the survival tail.
𝗗𝗖𝗩𝗮𝘅-𝗟 𝗮𝗹𝗿𝗲𝗮𝗱𝘆 𝗵𝗮𝘀 𝗮 𝗺𝗲𝗮𝘀𝘂𝗿𝗲𝗱 𝗳𝗶𝘃𝗲-𝘆𝗲𝗮𝗿 𝘁𝗮𝗶𝗹.
Northwest’s phase III publication reported five-year survival of 13.0% versus 5.7% in newly diagnosed glioblastoma, compared with external controls.
At recurrence, median survival was 13.2 months versus 7.8 months.
Across 2,151 doses, investigators reported five serious adverse events considered at least possibly treatment-related, with no evidence of autoimmune reactions or cytokine storm.
The recurrence finding adds another important insight: those vaccines were manufactured from the original tumour. Forty-six of the 64 crossover patients had no second surgery.
The original tumour material remained the basis of treatment after recurrence.
DCVax-L’s phase III schedule also continued beyond initial priming, with repeat doses through month 30. That provides a rationale for studying reinforcement of the response. Comparing cell counts across different products cannot establish comparative potency; what matters is the immune response those cells generate.
doi.org/10.1001/jamaoncol.20…
𝗡𝗼𝗿𝘁𝗵𝘄𝗲𝘀𝘁 𝗵𝗮𝘀 𝗰𝗼𝗻𝘁𝗶𝗻𝘂𝗲𝗱 𝗱𝗲𝘃𝗲𝗹𝗼𝗽𝗶𝗻𝗴 𝘁𝗵𝗲 𝗲𝘃𝗶𝗱𝗲𝗻𝗰𝗲.
In July 2026, Bosch presented updated analyses using individual patient data. Northwest reported that independent statisticians applied propensity-score matching and inverse-probability weighting.
The survival advantage persisted across methods and comparator datasets. Matching yielded median advantages of 3.4–6.3 months.
More detailed comparisons strengthened the reported signal. Full publication will allow independent scrutiny.
nwbio.com/northwest-biothera…
The company’s broader development programme follows the same biological logic:
Prepare effective dendritic cells.
Present a broad range of tumour targets.
Generate and, where appropriate, expand tumour-reactive cells.
Help them enter the tumour.
Address suppression and study checkpoint timing.
Investigate how to reinforce and sustain the response.
Northwest has licensed complementary technologies developed by Kalinski’s teams. DCVax-Direct explores acquiring tumour material inside the body. Its Flaskworks/Eden programme addresses the manufacturing capacity needed to deliver personalised cell treatment more widely.
These programmes require their own validation. Their significance is the connected strategy: improving the instructor, supporting the responding cells and building the means to manufacture treatment at scale.
nwbio.com/northwest-biothera…
𝗧𝗵𝗲 𝗽𝗲𝗼𝗽𝗹𝗲 𝘄𝗵𝗼 𝗯𝘂𝗶𝗹𝘁 𝘁𝗵𝗶𝘀 𝗽𝗿𝗼𝗴𝗿𝗮𝗺𝗺𝗲 𝘀𝗵𝗼𝘂𝗹𝗱 𝗯𝗲 𝗵𝗲𝗮𝗿𝗱.
The UK application was submitted in December 2023. In July 2026, Northwest reported MHRA confirmation that it remained under review and had not been refused.
sec.gov/Archives/edgar/data/…
Siobhain, please invite Northwest, Dr. Boynton, Dr. Bosch and Professor Ashkan to explain the evidence and the remaining steps directly to your campaign and parliamentary colleagues.
Then ask government and the company for a clear account of what remains unresolved, who must resolve it, and when a decision can be reached.
Press for a practical access plan alongside that work.
DCVax-L’s survival findings, safety record and biological rationale make a compelling case for its potential role as a treatment foundation. The people who developed it and the clinicians who tested it can explain that case in detail.
𝗘𝘃𝗲𝗿𝘆 𝗿𝗲𝗺𝗮𝗶𝗻𝗶𝗻𝗴 𝗿𝗲𝗾𝘂𝗶𝗿𝗲𝗺𝗲𝗻𝘁 𝗻𝗲𝗲𝗱𝘀 𝗮𝗻 𝗼𝘄𝗻𝗲𝗿, 𝗮 𝗻𝗲𝘅𝘁 𝘀𝘁𝗲𝗽 𝗮𝗻𝗱 𝗮 𝘁𝗶𝗺𝗲𝘁𝗮𝗯𝗹𝗲.
𝗙𝗮𝗺𝗶𝗹𝗶𝗲𝘀 𝗮𝗿𝗲 𝗺𝗲𝗮𝘀𝘂𝗿𝗶𝗻𝗴 𝘁𝗵𝗮𝘁 𝘁𝗶𝗺𝗲 𝗶𝗻 𝗯𝗶𝗿𝘁𝗵𝗱𝗮𝘆𝘀, 𝗴𝗿𝗮𝗱𝘂𝗮𝘁𝗶𝗼𝗻𝘀 𝗮𝗻𝗱 𝗮𝗻𝗼𝘁𝗵𝗲𝗿 𝗺𝗼𝗿𝗻𝗶𝗻𝗴 𝘁𝗼𝗴𝗲𝘁𝗵𝗲𝗿.
xitter.cf/andrewcaravello/status…
Mo retweeted

Kid…if it’s glioblastoma—DCVaxL by Northwest Bio is available in the UK. Patients are living 15+ years after being given 3 months to live. It’s groundbreaking treatment with no side effects. 🙏
Mo retweeted
Braelyn had some wonderful surprises waiting in her P.O. Box! ❤️📬
First, a beautiful card and incredibly generous gift from Max, right here in our home state of South Carolina. Max can relate personally to some of the challenges Braelyn is facing, and he shared how much he has been able to overcome through lots and lots of practice. That was incredibly encouraging for Braelyn to hear. ❤️ Thank you, Max, for sharing your story with her—and for your amazing generosity.
And then there’s Charles… 😂🦞
Apparently Charles has been paying attention, because he sent Braelyn the PERFECT Rock Lobster shirt AND her very own stuffed lobster.
She is now fully equipped to rock out to that irrita—
I mean, AMAZING song. 😑😂
Mom is thrilled. Absolutely thrilled.
Braelyn, however, thinks this is fantastic. 😂🦞🎶
Thank you, Charles!! And thank you to everyone who continues to send Braelyn cards, encouragement and little surprises. She truly loves checking her P.O. Box, and you have no idea how much these acts of kindness mean to her—and to us. ❤️


Mo retweeted
I started finding more long-term survivors.
This was probably the biggest change in my thinking.@ThomasOwenMcCa1 wasn’t alone.
Brad Silver received DCVax-L in one of the earliest trials after being diagnosed with GBM in his early 30s. He’s now a 23-year survivor.
Jamil Newirth was diagnosed at 32 and given approximately 17 months to live. He received UCLA’s personalized dendritic-cell vaccine and was profiled by UCLA more than a decade later, alive and thriving.
Sarah Rigby was diagnosed with GBM in 2011 and has been documented more than 15 years later as a long-term DCVax patient.
Nigel French was diagnosed with GBM in 2015, entered the DCVax-L trial at King’s College Hospital and was subsequently documented in long-term remission.
Kat Charles was diagnosed with grade 4 GBM in 2013 and at one point was told she had only three months to live. She later obtained a personalized dendritic-cell vaccine and continued receiving maintenance booster injections. More than a decade later, hers remains an extraordinary long-term-survivor story.
And I found other early UCLA dendritic-cell-vaccine survivors, including Jennifer Sugioka, Elijah Luyten and Gallia Kistler.
Suddenly Thomas didn’t look like one isolated anomaly anymore.
I was finding a group of people who had received this type of dendritic-cell vaccine and experienced extraordinary survival — 10 years, 12 years, 20-plus years — including patients with many years without recurrence.
And there is something especially important about these early survivors:
Many of them didn’t receive Hiltonol.
Some were treated years before the later UCLA study combining dendritic-cell vaccination with poly-ICLC.
In other words, the extraordinary long-term survivors already existed before these newer combinations were being used.
And that made the newer research even more exciting to me.
If some patients became 10-, 15- and even 20-plus-year survivors with the earlier vaccine approaches, what might be possible if researchers can now strengthen that immune response even further?
That’s the question that gives me hope.
Then came Marnix Bosch’s July 3, 2026 presentation.
At the British Neuro-Oncology Society meeting, Bosch presented new analyses using individual-patient data that hadn’t been available for the original Phase III analysis.
Researchers were now able to match DCVax patients much more precisely with patients from three randomized GBM trials based on important prognostic characteristics.
Across several propensity-score-matching approaches, the estimated survival advantage associated with DCVax-L was 3.4 to 6.3 months, rather than the original 2.8 months. Other statistical approaches produced similar results.
Their overall conclusion was that the original analysis had likely underestimated the survival benefit associated with DCVax-L.
Was that encouraging to me?
Absolutely.
But I want to be honest: an extra handful of months still isn’t what gives me hope.
Whether the median advantage is three months or six months, I don’t want six extra months for my daughter.
I want her to live a long, full life.
What the newer analysis did was strengthen my confidence that DCVax has a real treatment effect and that its original benefit may have been underestimated.
But my hope comes from the long tail.
At five years, 13% of newly diagnosed GBM patients receiving DCVax were alive compared with 5.7% of the external controls — more than double.
And now I know of some of the people represented by that tail.
Brad.
Thomas.
Jamil.
Sarah.
Nigel.
Kat.
Jennifer.
Elijah.
Gallia.
Those are the people I think about.
Mo retweeted

Urge Northwest Biotherapeutics for transparent DCVax-L MAA update - Sign the Petition! c.org/ZZmqB8JpjC via @Change $NWBO


But here's the interesting part:
“Unless we have the company’s agreement, we cannot share information regarding an application.”
Mo retweeted
It’s heartbreaking to think of the number of GBM patients who have died over this period of time. I wonder how many would still be here if they had an opportunity to receive this treatment.
Mo retweeted

$NWBO
Could license and access land on the same day?
@andrewcaravello asks what if the nearly three years DCVax-L has been before the UK regulator also includes the NHS payment work that used to start only after a licence?
$NWBO #DCVax #DCVaxForBraelyn
𝗧𝗛𝗘 𝗦𝗘𝗖𝗢𝗡𝗗 𝗖𝗟𝗢𝗖𝗞
𝗪𝗵𝗮𝘁 𝗶𝗳 𝘄𝗲 𝗵𝗮𝘃𝗲 𝗯𝗲𝗲𝗻 𝗺𝗲𝗮𝘀𝘂𝗿𝗶𝗻𝗴 𝘁𝗵𝗲 𝗗𝗖𝗩𝗮𝘅-𝗟 “𝗱𝗲𝗹𝗮𝘆” 𝗮𝗴𝗮𝗶𝗻𝘀𝘁 𝘁𝗵𝗲 𝘄𝗿𝗼𝗻𝗴 𝗳𝗶𝗻𝗶𝘀𝗵 𝗹𝗶𝗻𝗲?
DCVax-L’s UK Marketing Authorisation Application was submitted on December 20, 2023.
Today marks 1,016 calendar days.
The obvious question has always been:
“Why is MHRA taking so long?”
I think there may be a better one.
𝗪𝗵𝗮𝘁 𝗶𝗳 𝗮 𝘀𝗲𝗰𝗼𝗻𝗱 𝗰𝗹𝗼𝗰𝗸 𝗵𝗮𝘀 𝗯𝗲𝗲𝗻 𝗿𝘂𝗻𝗻𝗶𝗻𝗴 𝗯𝗲𝘀𝗶𝗱𝗲 𝘁𝗵𝗲 𝗳𝗶𝗿𝘀𝘁?
Under the traditional UK model, the process was largely sequential:
𝗠𝗛𝗥𝗔 𝗿𝗲𝘃𝗶𝗲𝘄
↓
𝗠𝗮𝗿𝗸𝗲𝘁𝗶𝗻𝗴 𝗮𝘂𝘁𝗵𝗼𝗿𝗶𝘀𝗮𝘁𝗶𝗼𝗻
↓
𝗡𝗜𝗖𝗘 𝗮𝗽𝗽𝗿𝗮𝗶𝘀𝗮𝗹
↓
𝗡𝗜𝗖𝗘 𝗴𝘂𝗶𝗱𝗮𝗻𝗰𝗲
↓
𝗡𝗛𝗦 𝗳𝘂𝗻𝗱𝗶𝗻𝗴 𝗮𝗻𝗱 𝗮𝗰𝗰𝗲𝘀𝘀
Approval was never the same thing as access.
NICE says there has typically been about a 90-day gap between MHRA marketing authorisation and NICE guidance.
The new MHRA-NICE Aligned Pathway is specifically designed to remove that gap.
Instead of running the clocks one after another, Britain can now run them in parallel.
𝗠𝗛𝗥𝗔 𝗿𝗲𝘃𝗶𝗲𝘄
↕
𝗡𝗜𝗖𝗘 𝗮𝗽𝗽𝗿𝗮𝗶𝘀𝗮𝗹
↓
𝗟𝗶𝗰𝗲𝗻𝗰𝗲 + 𝗡𝗜𝗖𝗘 𝗴𝘂𝗶𝗱𝗮𝗻𝗰𝗲
↓
𝗔 𝘀𝗵𝗼𝗿𝘁𝗲𝗿 𝗿𝗼𝗮𝗱 𝘁𝗼 𝗳𝘂𝗻𝗱𝗲𝗱 𝗡𝗛𝗦 𝗮𝗰𝗰𝗲𝘀𝘀
NICE can now hold appraisal committee meetings before marketing authorisation. It can publish draft guidance before authorisation. It can even complete final draft guidance before MHRA makes its decision, with the recommendation conditional upon the licence ultimately being granted.
For medicines that remain on schedule, the stated objective is simultaneous publication of the MHRA licence and NICE guidance.
The government estimates this can remove 3 to 6 months from the journey to patients.
𝗕𝘂𝘁 𝗵𝗲𝗿𝗲 𝗶𝘀 𝘄𝗵𝗲𝗿𝗲 𝗗𝗖𝗩𝗮𝘅-𝗟 𝗯𝗲𝗰𝗼𝗺𝗲𝘀 𝗽𝗮𝗿𝘁𝗶𝗰𝘂𝗹𝗮𝗿𝗹𝘆 𝗶𝗻𝘁𝗲𝗿𝗲𝘀𝘁𝗶𝗻𝗴.
The second clock did not suddenly appear in 2026.
𝗕𝘆 𝗦𝗲𝗽𝘁𝗲𝗺𝗯𝗲𝗿 𝟮𝟬𝟮𝟰, 𝗡𝗼𝗿𝘁𝗵𝘄𝗲𝘀𝘁 𝗕𝗶𝗼𝘁𝗵𝗲𝗿𝗮𝗽𝗲𝘂𝘁𝗶𝗰𝘀 𝘄𝗮𝘀 𝗮𝗹𝗿𝗲𝗮𝗱𝘆 𝘄𝗼𝗿𝗸𝗶𝗻𝗴 𝗼𝗻 𝗿𝗲𝗶𝗺𝗯𝘂𝗿𝘀𝗲𝗺𝗲𝗻𝘁.
The company disclosed that it had selected specialized reimbursement consultants, executed contracts, and begun the first stage of the process.
That work included health economics and outcomes analyses, analysis of the clinical landscape, engagement with experts and stakeholders, and other preparations necessary for reimbursement review.
That is not theory.
That is Northwest telling us that while one process was occurring at MHRA, another process was already being built around what happens 𝗮𝗳𝘁𝗲𝗿 regulatory approval.
And there was already infrastructure connecting those worlds.
MHRA’s Operational Information Sharing system allows an applicant, with consent, to let MHRA share administrative information with NICE and NHS England, including the regulatory route, submission date, estimated MHRA decision date, and ultimately the actual decision.
The stated purpose is to allow the health system to prepare its own processes more efficiently and reduce avoidable delays in patient access.
We do not know publicly whether Northwest provided that consent.
But the channel exists.
And DCVax-L was not arriving at NICE as a new product.
It already had 𝗜𝗗𝟴𝟯𝟲.
NICE had referred the topic years earlier, conducted scope work, consulted stakeholders, and invited the company into the appraisal process.
In fact, in the 2018 ID836 scope documents, NICE was already stating that it aimed to publish guidance on cancer drugs within 90 days of marketing authorisation.
So the regulatory and reimbursement tracks around DCVax-L have a much longer history than the current aligned pathway.
Then the public chronology becomes very interesting.
𝗔𝗽𝗿𝗶𝗹 𝟮𝟴, 𝟮𝟬𝟮𝟱.
The UK government tells Parliament that NICE aims, wherever possible, to issue recommendations close to the time of MHRA licensing.
Then it confirms something specific to DCVax-L:
NICE is already in discussions with the manufacturer about a potential appraisal, subject to licensing.
That is important.
It means the NICE clock was publicly visible months before the formal aligned pathway opened.
𝗢𝗰𝘁𝗼𝗯𝗲𝗿 𝟭𝟬, 𝟮𝟬𝟮𝟱.
MHRA and NICE open the aligned pathway to early adopters six months ahead of schedule.
And they specifically invite companies whose products already have NICE technology appraisals scheduled to contact NICE if their medicine may be suitable.
DCVax-L already had exactly that kind of NICE history through ID836.
The new system offers priority NICE scheduling and coordinates licensing and value assessment so the decisions can be published together.
This does not automatically move an existing product onto the pathway.
The company has to participate.
We do not have public proof that Northwest did.
But DCVax-L clearly sits inside the category NICE was actively seeking.
𝗗𝗲𝗰𝗲𝗺𝗯𝗲𝗿 𝟴, 𝟮𝟬𝟮𝟱.
The government makes another unusually specific statement about DCVax-L:
The application “is not affected by any historical backlogs.”
Then it again confirms that NICE is in discussions with Northwest Biotherapeutics about a potential appraisal subject to licensing.
Whatever is consuming the time, the UK government has therefore specifically told us what it is not.
It is not simply the old MHRA backlog.
𝗠𝗮𝗿𝗰𝗵 𝟭𝟴, 𝟮𝟬𝟮𝟲.
The government repeats that DCVax-L remains under MHRA assessment and again states that NICE aims to issue recommendations close to licensing and is discussing a potential DCVax-L appraisal with Northwest.
𝗔𝗽𝗿𝗶𝗹 𝟮𝟬𝟮𝟲.
The aligned pathway becomes fully operational.
At essentially the same time, another variable changes.
NICE raises the standard cost-effectiveness range from £20,000 to £30,000 per QALY to £25,000 to £35,000 per QALY.
And critically, NICE says the new thresholds apply not just to future appraisals, but also to technology appraisals already underway.
For a personalized living-cell therapy with an unusual upfront manufacturing cost structure, that change is potentially material.
It does not guarantee a favorable NICE decision.
But it unquestionably changes the economic framework within which an appraisal occurring today would be judged.
𝗝𝘂𝗹𝘆 𝟮𝟬𝟮𝟲.
Northwest presents new individual-patient-level survival analyses at BNOS using propensity score matching and inverse probability weighting against external randomized-trial controls.
The analyses were performed by independent statisticians and produced results broadly consistent across multiple comparator datasets and analytical approaches.
Those methods are also highly relevant to health technology assessment because they address one of the central problems with external controls: balancing measured confounders between treated patients and comparison populations.
That does not establish that the BNOS analyses were created for NICE.
But the same evidence can plainly matter to both clocks.
𝗦𝗲𝗽𝘁𝗲𝗺𝗯𝗲𝗿 𝟮𝟴, 𝟮𝟬𝟮𝟲.
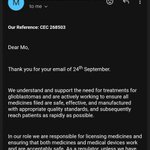
I wrote directly to MHRA asking about the extraordinarily long DCVax-L process.
MHRA responded that it is:
“working actively on this application”
and is:
“progressing this application as rapidly as possible and in collaboration with the company.”
MHRA also specifically directed me to NICE’s DCVax-L appraisal, ID836.
That does not prove DCVax-L is on the aligned pathway.
But it establishes something important at the very end of this timeline.
𝗧𝗵𝗶𝘀 𝗶𝘀 𝗻𝗼𝘁 𝗮 𝗱𝗲𝗮𝗱 𝗮𝗽𝗽𝗹𝗶𝗰𝗮𝘁𝗶𝗼𝗻 𝘀𝗶𝘁𝘁𝗶𝗻𝗴 𝗶𝗻 𝗮 𝗾𝘂𝗲𝘂𝗲.
MHRA says it is actively working on it, rapidly, and in collaboration with Northwest.
Two days later, on 𝗦𝗲𝗽𝘁𝗲𝗺𝗯𝗲𝗿 𝟯𝟬, NICE published its latest report on the aligned pathway.
NICE disclosed that 90 topics across 49 therapeutic areas have now been scheduled, including products from both multinational companies and smaller and medium-sized enterprises.
The names are not disclosed publicly.
MHRA and NICE aligned pathway- how it's working in practice
And this is perhaps the most important structural fact of all.
NICE now says openly that it works with MHRA so that final guidance can be published at the same time as marketing authorisation when companies can meet the required timings.
Companies are asked to keep UK PharmaScan current, update both organizations on regulatory plans, and permit operational and planning information to be shared between NICE and MHRA.
That is not two agencies independently happening to finish around the same time.
𝗧𝗵𝗮𝘁 𝗶𝘀 𝗮 𝘀𝘆𝘀𝘁𝗲𝗺 𝗯𝘂𝗶𝗹𝘁 𝘁𝗼 𝘀𝘆𝗻𝗰𝗵𝗿𝗼𝗻𝗶𝘇𝗲 𝘁𝘄𝗼 𝗰𝗹𝗼𝗰𝗸𝘀.
And that brings me to the thesis.
𝗧𝗵𝗲 𝗠𝗛𝗥𝗔-𝗡𝗜𝗖𝗘 𝗔𝗹𝗶𝗴𝗻𝗲𝗱 𝗣𝗮𝘁𝗵𝘄𝗮𝘆 𝗱𝗶𝗱 𝗻𝗼𝘁 𝗰𝗮𝘂𝘀𝗲 𝘁𝗵𝗲 𝟭,𝟬𝟭𝟲-𝗱𝗮𝘆 𝗗𝗖𝗩𝗮𝘅-𝗟 𝗿𝗲𝘃𝗶𝗲𝘄.
It could not have.
The application had already been under review for nearly two years when the early-adopter phase began.
And I have found no evidence that MHRA completed its scientific review and deliberately placed an otherwise-ready licence on a shelf waiting for NICE.
That is not how the aligned pathway is designed.
𝗕𝘂𝘁 𝘁𝗵𝗮𝘁 𝗺𝗮𝘆 𝗯𝗲 𝘁𝗵𝗲 𝘄𝗿𝗼𝗻𝗴 𝘄𝗮𝘆 𝘁𝗼 𝘁𝗵𝗶𝗻𝗸 𝗮𝗯𝗼𝘂𝘁 𝘁𝗵𝗲 𝗱𝗲𝗹𝗮𝘆.
The more interesting possibility is that the value of the remaining time changed.
If NICE appraisal preparation, health-economic work, reimbursement planning, regulatory information sharing, manufacturing readiness, and NHS access planning are occurring during the MHRA review, then every additional calendar month before the visible licensing decision is not necessarily another month added to the ultimate patient-access timeline.
Some of that work is time that the old system would have forced everyone to spend 𝗮𝗳𝘁𝗲𝗿 approval.
That is why simply counting days to an MHRA announcement may now tell only half the story.
𝗧𝘄𝗼 𝗰𝗹𝗼𝗰𝗸𝘀.
𝗦𝗮𝗺𝗲 𝗰𝗮𝗹𝗲𝗻𝗱𝗮𝗿.
And for DCVax-L, this distinction could matter far more than it would for an ordinary pill.
Northwest itself says DCVax-L is a personalized living-cell product with substantial manufacturing costs incurred upfront, specialized distribution requirements, and potentially complex reimbursement arrangements. The company explicitly warns that obtaining workable reimbursement will be essential to commercialization.
For a therapy like this, a licence alone solves only part of the problem.
The real finish line is not:
𝗖𝗔𝗡 𝗪𝗘 𝗦𝗘𝗟𝗟 𝗜𝗧?
It is:
𝗖𝗔𝗡 𝗧𝗛𝗘 𝗡𝗛𝗦 𝗣𝗔𝗬 𝗙𝗢𝗥 𝗜𝗧, 𝗖𝗢𝗠𝗠𝗜𝗦𝗦𝗜𝗢𝗡 𝗜𝗧, 𝗔𝗡𝗗 𝗗𝗘𝗟𝗜𝗩𝗘𝗥 𝗜𝗧?
Because once NICE recommends a medicine, the NHS is normally legally required to fund it within three months of final guidance.
So compare the two outcomes:
𝗢𝗟𝗗 𝗙𝗜𝗡𝗜𝗦𝗛
Licence
↓
NICE appraisal
↓
Guidance
↓
Funding
𝗡𝗘𝗪 𝗙𝗜𝗡𝗜𝗦𝗛
Licence + NICE guidance
↓
Funding
That is a very different endpoint.
𝗡𝗼𝘁 𝗷𝘂𝘀𝘁 𝗽𝗲𝗿𝗺𝗶𝘀𝘀𝗶𝗼𝗻 𝘁𝗼 𝘀𝗲𝗹𝗹.
𝗔 𝗽𝗮𝘁𝗵 𝘁𝗼 𝗯𝗲 𝗽𝗮𝗶𝗱.
𝗡𝗼𝘁 𝗷𝘂𝘀𝘁 𝗮𝗽𝗽𝗿𝗼𝘃𝗮𝗹.
𝗔𝗰𝗰𝗲𝘀𝘀.
𝗛𝗢𝗪 𝗧𝗢 𝗧𝗘𝗦𝗧 𝗧𝗛𝗘 𝗧𝗛𝗘𝗦𝗜𝗦
This remains a hypothesis.
I cannot find public evidence proving that DCVax-L is one of the 90 topics scheduled through the aligned pathway.
An old NICE appraisal does not automatically migrate into the new pathway.
Northwest would have had to engage with the process.
And NICE explicitly acknowledges that some complex products may use alternate scheduling, with committee consideration occurring only after marketing authorisation.
So there are two versions.
𝗧𝗛𝗘 𝗦𝗧𝗥𝗢𝗡𝗚 𝗩𝗘𝗥𝗦𝗜𝗢𝗡
DCVax-L is formally proceeding through aligned scheduling, and NICE activity becomes visible before MHRA authorisation, potentially allowing NICE guidance to land with the licence.
𝗧𝗛𝗘 𝗪𝗘𝗔𝗞𝗘𝗥 𝗩𝗘𝗥𝗦𝗜𝗢𝗡
The licence arrives first, but NICE follows unusually quickly because substantial appraisal and reimbursement preparation has already occurred behind it.
Either way, the place to watch is:
𝗜𝗗𝟴𝟯𝟲.
It remains listed by NICE as “In development” with publication timing TBC.
If substantive NICE activity appears before MHRA approval, the strong version becomes much more compelling.
If MHRA approves DCVax-L and ID836 then remains dormant for months, this thesis loses much of its force.
But after following the evidence from the company, Parliament, MHRA and NICE, I no longer think the most revealing question is:
“Why has MHRA taken 1,016 days?”
I think it is this:
𝗛𝗢𝗪 𝗠𝗨𝗖𝗛 𝗢𝗙 𝗪𝗛𝗔𝗧 𝗖𝗢𝗠𝗘𝗦 𝗔𝗙𝗧𝗘𝗥 𝗔𝗣𝗣𝗥𝗢𝗩𝗔𝗟 𝗛𝗔𝗦 𝗔𝗟𝗥𝗘𝗔𝗗𝗬 𝗛𝗔𝗣𝗣𝗘𝗡𝗘𝗗?
𝗧𝗵𝗮𝘁 𝗶𝘀 𝘁𝗵𝗲 𝘀𝗲𝗰𝗼𝗻𝗱 𝗰𝗹𝗼𝗰𝗸.
Long $NWBO.
𝗔 𝗵𝘆𝗽𝗼𝘁𝗵𝗲𝘀𝗶𝘀. 𝗡𝗼𝘁 𝗮 𝗽𝗿𝗲𝗱𝗶𝗰𝘁𝗶𝗼𝗻.


Mo retweeted

$NWBO #DCVax #DCVaxForBraelyn
𝗧𝗛𝗘 𝗦𝗘𝗖𝗢𝗡𝗗 𝗖𝗟𝗢𝗖𝗞
𝗪𝗵𝗮𝘁 𝗶𝗳 𝘄𝗲 𝗵𝗮𝘃𝗲 𝗯𝗲𝗲𝗻 𝗺𝗲𝗮𝘀𝘂𝗿𝗶𝗻𝗴 𝘁𝗵𝗲 𝗗𝗖𝗩𝗮𝘅-𝗟 “𝗱𝗲𝗹𝗮𝘆” 𝗮𝗴𝗮𝗶𝗻𝘀𝘁 𝘁𝗵𝗲 𝘄𝗿𝗼𝗻𝗴 𝗳𝗶𝗻𝗶𝘀𝗵 𝗹𝗶𝗻𝗲?
DCVax-L’s UK Marketing Authorisation Application was submitted on December 20, 2023.
Today marks 1,016 calendar days.
The obvious question has always been:
“Why is MHRA taking so long?”
I think there may be a better one.
𝗪𝗵𝗮𝘁 𝗶𝗳 𝗮 𝘀𝗲𝗰𝗼𝗻𝗱 𝗰𝗹𝗼𝗰𝗸 𝗵𝗮𝘀 𝗯𝗲𝗲𝗻 𝗿𝘂𝗻𝗻𝗶𝗻𝗴 𝗯𝗲𝘀𝗶𝗱𝗲 𝘁𝗵𝗲 𝗳𝗶𝗿𝘀𝘁?
Under the traditional UK model, the process was largely sequential:
𝗠𝗛𝗥𝗔 𝗿𝗲𝘃𝗶𝗲𝘄
↓
𝗠𝗮𝗿𝗸𝗲𝘁𝗶𝗻𝗴 𝗮𝘂𝘁𝗵𝗼𝗿𝗶𝘀𝗮𝘁𝗶𝗼𝗻
↓
𝗡𝗜𝗖𝗘 𝗮𝗽𝗽𝗿𝗮𝗶𝘀𝗮𝗹
↓
𝗡𝗜𝗖𝗘 𝗴𝘂𝗶𝗱𝗮𝗻𝗰𝗲
↓
𝗡𝗛𝗦 𝗳𝘂𝗻𝗱𝗶𝗻𝗴 𝗮𝗻𝗱 𝗮𝗰𝗰𝗲𝘀𝘀
Approval was never the same thing as access.
NICE says there has typically been about a 90-day gap between MHRA marketing authorisation and NICE guidance.
The new MHRA-NICE Aligned Pathway is specifically designed to remove that gap.
Instead of running the clocks one after another, Britain can now run them in parallel.
𝗠𝗛𝗥𝗔 𝗿𝗲𝘃𝗶𝗲𝘄
↕
𝗡𝗜𝗖𝗘 𝗮𝗽𝗽𝗿𝗮𝗶𝘀𝗮𝗹
↓
𝗟𝗶𝗰𝗲𝗻𝗰𝗲 + 𝗡𝗜𝗖𝗘 𝗴𝘂𝗶𝗱𝗮𝗻𝗰𝗲
↓
𝗔 𝘀𝗵𝗼𝗿𝘁𝗲𝗿 𝗿𝗼𝗮𝗱 𝘁𝗼 𝗳𝘂𝗻𝗱𝗲𝗱 𝗡𝗛𝗦 𝗮𝗰𝗰𝗲𝘀𝘀
NICE can now hold appraisal committee meetings before marketing authorisation. It can publish draft guidance before authorisation. It can even complete final draft guidance before MHRA makes its decision, with the recommendation conditional upon the licence ultimately being granted.
For medicines that remain on schedule, the stated objective is simultaneous publication of the MHRA licence and NICE guidance.
The government estimates this can remove 3 to 6 months from the journey to patients.
𝗕𝘂𝘁 𝗵𝗲𝗿𝗲 𝗶𝘀 𝘄𝗵𝗲𝗿𝗲 𝗗𝗖𝗩𝗮𝘅-𝗟 𝗯𝗲𝗰𝗼𝗺𝗲𝘀 𝗽𝗮𝗿𝘁𝗶𝗰𝘂𝗹𝗮𝗿𝗹𝘆 𝗶𝗻𝘁𝗲𝗿𝗲𝘀𝘁𝗶𝗻𝗴.
The second clock did not suddenly appear in 2026.
𝗕𝘆 𝗦𝗲𝗽𝘁𝗲𝗺𝗯𝗲𝗿 𝟮𝟬𝟮𝟰, 𝗡𝗼𝗿𝘁𝗵𝘄𝗲𝘀𝘁 𝗕𝗶𝗼𝘁𝗵𝗲𝗿𝗮𝗽𝗲𝘂𝘁𝗶𝗰𝘀 𝘄𝗮𝘀 𝗮𝗹𝗿𝗲𝗮𝗱𝘆 𝘄𝗼𝗿𝗸𝗶𝗻𝗴 𝗼𝗻 𝗿𝗲𝗶𝗺𝗯𝘂𝗿𝘀𝗲𝗺𝗲𝗻𝘁.
The company disclosed that it had selected specialized reimbursement consultants, executed contracts, and begun the first stage of the process.
That work included health economics and outcomes analyses, analysis of the clinical landscape, engagement with experts and stakeholders, and other preparations necessary for reimbursement review.
That is not theory.
That is Northwest telling us that while one process was occurring at MHRA, another process was already being built around what happens 𝗮𝗳𝘁𝗲𝗿 regulatory approval.
And there was already infrastructure connecting those worlds.
MHRA’s Operational Information Sharing system allows an applicant, with consent, to let MHRA share administrative information with NICE and NHS England, including the regulatory route, submission date, estimated MHRA decision date, and ultimately the actual decision.
The stated purpose is to allow the health system to prepare its own processes more efficiently and reduce avoidable delays in patient access.
We do not know publicly whether Northwest provided that consent.
But the channel exists.
And DCVax-L was not arriving at NICE as a new product.
It already had 𝗜𝗗𝟴𝟯𝟲.
NICE had referred the topic years earlier, conducted scope work, consulted stakeholders, and invited the company into the appraisal process.
In fact, in the 2018 ID836 scope documents, NICE was already stating that it aimed to publish guidance on cancer drugs within 90 days of marketing authorisation.
So the regulatory and reimbursement tracks around DCVax-L have a much longer history than the current aligned pathway.
Then the public chronology becomes very interesting.
𝗔𝗽𝗿𝗶𝗹 𝟮𝟴, 𝟮𝟬𝟮𝟱.
The UK government tells Parliament that NICE aims, wherever possible, to issue recommendations close to the time of MHRA licensing.
Then it confirms something specific to DCVax-L:
NICE is already in discussions with the manufacturer about a potential appraisal, subject to licensing.
That is important.
It means the NICE clock was publicly visible months before the formal aligned pathway opened.
𝗢𝗰𝘁𝗼𝗯𝗲𝗿 𝟭𝟬, 𝟮𝟬𝟮𝟱.
MHRA and NICE open the aligned pathway to early adopters six months ahead of schedule.
And they specifically invite companies whose products already have NICE technology appraisals scheduled to contact NICE if their medicine may be suitable.
DCVax-L already had exactly that kind of NICE history through ID836.
The new system offers priority NICE scheduling and coordinates licensing and value assessment so the decisions can be published together.
This does not automatically move an existing product onto the pathway.
The company has to participate.
We do not have public proof that Northwest did.
But DCVax-L clearly sits inside the category NICE was actively seeking.
𝗗𝗲𝗰𝗲𝗺𝗯𝗲𝗿 𝟴, 𝟮𝟬𝟮𝟱.
The government makes another unusually specific statement about DCVax-L:
The application “is not affected by any historical backlogs.”
Then it again confirms that NICE is in discussions with Northwest Biotherapeutics about a potential appraisal subject to licensing.
Whatever is consuming the time, the UK government has therefore specifically told us what it is not.
It is not simply the old MHRA backlog.
𝗠𝗮𝗿𝗰𝗵 𝟭𝟴, 𝟮𝟬𝟮𝟲.
The government repeats that DCVax-L remains under MHRA assessment and again states that NICE aims to issue recommendations close to licensing and is discussing a potential DCVax-L appraisal with Northwest.
𝗔𝗽𝗿𝗶𝗹 𝟮𝟬𝟮𝟲.
The aligned pathway becomes fully operational.
At essentially the same time, another variable changes.
NICE raises the standard cost-effectiveness range from £20,000 to £30,000 per QALY to £25,000 to £35,000 per QALY.
And critically, NICE says the new thresholds apply not just to future appraisals, but also to technology appraisals already underway.
For a personalized living-cell therapy with an unusual upfront manufacturing cost structure, that change is potentially material.
It does not guarantee a favorable NICE decision.
But it unquestionably changes the economic framework within which an appraisal occurring today would be judged.
𝗝𝘂𝗹𝘆 𝟮𝟬𝟮𝟲.
Northwest presents new individual-patient-level survival analyses at BNOS using propensity score matching and inverse probability weighting against external randomized-trial controls.
The analyses were performed by independent statisticians and produced results broadly consistent across multiple comparator datasets and analytical approaches.
Those methods are also highly relevant to health technology assessment because they address one of the central problems with external controls: balancing measured confounders between treated patients and comparison populations.
That does not establish that the BNOS analyses were created for NICE.
But the same evidence can plainly matter to both clocks.
𝗦𝗲𝗽𝘁𝗲𝗺𝗯𝗲𝗿 𝟮𝟴, 𝟮𝟬𝟮𝟲.
I wrote directly to MHRA asking about the extraordinarily long DCVax-L process.
MHRA responded that it is:
“working actively on this application”
and is:
“progressing this application as rapidly as possible and in collaboration with the company.”
MHRA also specifically directed me to NICE’s DCVax-L appraisal, ID836.
That does not prove DCVax-L is on the aligned pathway.
But it establishes something important at the very end of this timeline.
𝗧𝗵𝗶𝘀 𝗶𝘀 𝗻𝗼𝘁 𝗮 𝗱𝗲𝗮𝗱 𝗮𝗽𝗽𝗹𝗶𝗰𝗮𝘁𝗶𝗼𝗻 𝘀𝗶𝘁𝘁𝗶𝗻𝗴 𝗶𝗻 𝗮 𝗾𝘂𝗲𝘂𝗲.
MHRA says it is actively working on it, rapidly, and in collaboration with Northwest.
Two days later, on 𝗦𝗲𝗽𝘁𝗲𝗺𝗯𝗲𝗿 𝟯𝟬, NICE published its latest report on the aligned pathway.
NICE disclosed that 90 topics across 49 therapeutic areas have now been scheduled, including products from both multinational companies and smaller and medium-sized enterprises.
The names are not disclosed publicly.
MHRA and NICE aligned pathway- how it's working in practice
And this is perhaps the most important structural fact of all.
NICE now says openly that it works with MHRA so that final guidance can be published at the same time as marketing authorisation when companies can meet the required timings.
Companies are asked to keep UK PharmaScan current, update both organizations on regulatory plans, and permit operational and planning information to be shared between NICE and MHRA.
That is not two agencies independently happening to finish around the same time.
𝗧𝗵𝗮𝘁 𝗶𝘀 𝗮 𝘀𝘆𝘀𝘁𝗲𝗺 𝗯𝘂𝗶𝗹𝘁 𝘁𝗼 𝘀𝘆𝗻𝗰𝗵𝗿𝗼𝗻𝗶𝘇𝗲 𝘁𝘄𝗼 𝗰𝗹𝗼𝗰𝗸𝘀.
And that brings me to the thesis.
𝗧𝗵𝗲 𝗠𝗛𝗥𝗔-𝗡𝗜𝗖𝗘 𝗔𝗹𝗶𝗴𝗻𝗲𝗱 𝗣𝗮𝘁𝗵𝘄𝗮𝘆 𝗱𝗶𝗱 𝗻𝗼𝘁 𝗰𝗮𝘂𝘀𝗲 𝘁𝗵𝗲 𝟭,𝟬𝟭𝟲-𝗱𝗮𝘆 𝗗𝗖𝗩𝗮𝘅-𝗟 𝗿𝗲𝘃𝗶𝗲𝘄.
It could not have.
The application had already been under review for nearly two years when the early-adopter phase began.
And I have found no evidence that MHRA completed its scientific review and deliberately placed an otherwise-ready licence on a shelf waiting for NICE.
That is not how the aligned pathway is designed.
𝗕𝘂𝘁 𝘁𝗵𝗮𝘁 𝗺𝗮𝘆 𝗯𝗲 𝘁𝗵𝗲 𝘄𝗿𝗼𝗻𝗴 𝘄𝗮𝘆 𝘁𝗼 𝘁𝗵𝗶𝗻𝗸 𝗮𝗯𝗼𝘂𝘁 𝘁𝗵𝗲 𝗱𝗲𝗹𝗮𝘆.
The more interesting possibility is that the value of the remaining time changed.
If NICE appraisal preparation, health-economic work, reimbursement planning, regulatory information sharing, manufacturing readiness, and NHS access planning are occurring during the MHRA review, then every additional calendar month before the visible licensing decision is not necessarily another month added to the ultimate patient-access timeline.
Some of that work is time that the old system would have forced everyone to spend 𝗮𝗳𝘁𝗲𝗿 approval.
That is why simply counting days to an MHRA announcement may now tell only half the story.
𝗧𝘄𝗼 𝗰𝗹𝗼𝗰𝗸𝘀.
𝗦𝗮𝗺𝗲 𝗰𝗮𝗹𝗲𝗻𝗱𝗮𝗿.
And for DCVax-L, this distinction could matter far more than it would for an ordinary pill.
Northwest itself says DCVax-L is a personalized living-cell product with substantial manufacturing costs incurred upfront, specialized distribution requirements, and potentially complex reimbursement arrangements. The company explicitly warns that obtaining workable reimbursement will be essential to commercialization.
For a therapy like this, a licence alone solves only part of the problem.
The real finish line is not:
𝗖𝗔𝗡 𝗪𝗘 𝗦𝗘𝗟𝗟 𝗜𝗧?
It is:
𝗖𝗔𝗡 𝗧𝗛𝗘 𝗡𝗛𝗦 𝗣𝗔𝗬 𝗙𝗢𝗥 𝗜𝗧, 𝗖𝗢𝗠𝗠𝗜𝗦𝗦𝗜𝗢𝗡 𝗜𝗧, 𝗔𝗡𝗗 𝗗𝗘𝗟𝗜𝗩𝗘𝗥 𝗜𝗧?
Because once NICE recommends a medicine, the NHS is normally legally required to fund it within three months of final guidance.
So compare the two outcomes:
𝗢𝗟𝗗 𝗙𝗜𝗡𝗜𝗦𝗛
Licence
↓
NICE appraisal
↓
Guidance
↓
Funding
𝗡𝗘𝗪 𝗙𝗜𝗡𝗜𝗦𝗛
Licence + NICE guidance
↓
Funding
That is a very different endpoint.
𝗡𝗼𝘁 𝗷𝘂𝘀𝘁 𝗽𝗲𝗿𝗺𝗶𝘀𝘀𝗶𝗼𝗻 𝘁𝗼 𝘀𝗲𝗹𝗹.
𝗔 𝗽𝗮𝘁𝗵 𝘁𝗼 𝗯𝗲 𝗽𝗮𝗶𝗱.
𝗡𝗼𝘁 𝗷𝘂𝘀𝘁 𝗮𝗽𝗽𝗿𝗼𝘃𝗮𝗹.
𝗔𝗰𝗰𝗲𝘀𝘀.
𝗛𝗢𝗪 𝗧𝗢 𝗧𝗘𝗦𝗧 𝗧𝗛𝗘 𝗧𝗛𝗘𝗦𝗜𝗦
This remains a hypothesis.
I cannot find public evidence proving that DCVax-L is one of the 90 topics scheduled through the aligned pathway.
An old NICE appraisal does not automatically migrate into the new pathway.
Northwest would have had to engage with the process.
And NICE explicitly acknowledges that some complex products may use alternate scheduling, with committee consideration occurring only after marketing authorisation.
So there are two versions.
𝗧𝗛𝗘 𝗦𝗧𝗥𝗢𝗡𝗚 𝗩𝗘𝗥𝗦𝗜𝗢𝗡
DCVax-L is formally proceeding through aligned scheduling, and NICE activity becomes visible before MHRA authorisation, potentially allowing NICE guidance to land with the licence.
𝗧𝗛𝗘 𝗪𝗘𝗔𝗞𝗘𝗥 𝗩𝗘𝗥𝗦𝗜𝗢𝗡
The licence arrives first, but NICE follows unusually quickly because substantial appraisal and reimbursement preparation has already occurred behind it.
Either way, the place to watch is:
𝗜𝗗𝟴𝟯𝟲.
It remains listed by NICE as “In development” with publication timing TBC.
If substantive NICE activity appears before MHRA approval, the strong version becomes much more compelling.
If MHRA approves DCVax-L and ID836 then remains dormant for months, this thesis loses much of its force.
But after following the evidence from the company, Parliament, MHRA and NICE, I no longer think the most revealing question is:
“Why has MHRA taken 1,016 days?”
I think it is this:
𝗛𝗢𝗪 𝗠𝗨𝗖𝗛 𝗢𝗙 𝗪𝗛𝗔𝗧 𝗖𝗢𝗠𝗘𝗦 𝗔𝗙𝗧𝗘𝗥 𝗔𝗣𝗣𝗥𝗢𝗩𝗔𝗟 𝗛𝗔𝗦 𝗔𝗟𝗥𝗘𝗔𝗗𝗬 𝗛𝗔𝗣𝗣𝗘𝗡𝗘𝗗?
𝗧𝗵𝗮𝘁 𝗶𝘀 𝘁𝗵𝗲 𝘀𝗲𝗰𝗼𝗻𝗱 𝗰𝗹𝗼𝗰𝗸.
Long $NWBO.
𝗔 𝗵𝘆𝗽𝗼𝘁𝗵𝗲𝘀𝗶𝘀. 𝗡𝗼𝘁 𝗮 𝗽𝗿𝗲𝗱𝗶𝗰𝘁𝗶𝗼𝗻.

The MHRA-NICE aligned pathway is gathering pace, with the first medicine expected to complete its journey later this year.
Read our update on how same time decisions on licencing and value, and integrated scientific advice, are working in practice: brnw.ch/21x64rY

