









aksel retweeted

❌ Recettes : 35 milliards + 27 milliards + Abracadabra = 267 milliards.
C’est terminé pour Mélenchon.


aksel retweeted

To recap:
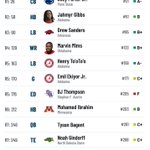
Cowboys get:
George Pickens
Broderick Jones
Joey Porter Jr.
2027 4th round pick
Steelers get:
2026 3rd round pick (Drew Allar)
2027 5th round pick
2027 3rd round pick
2027 6th round pick
2027 6th round pick
2028 2nd round pick


aksel retweeted

Uncertainty about treatment after T-DXd remains.
In a new French real-world series of 105 patients with HER2+ metastatic breast cancer treated with tucatinib + trastuzumab + capecitabine (TTC) after T-DXd, 92% received TTC in the third-line setting. Median PFS was 4.7 months, median OS 15.3 months, and ORR 29.6%. Brain metastases were present in 55% of patients, with a median PFS of 4.9 months in this group.
These findings are quite consistent with previous post–T-DXd TTC series and add to the accumulating evidence for tucatinib, particularly in patients with CNS disease.
But as T-DXd + pertuzumab moves into the first-line setting, the key question changes:
After first-line T-DXd + pertuzumab, should we use the previously unused taxane + trastuzumab + pertuzumab, or tucatinib + trastuzumab + capecitabine in the second line?
We currently have no comparative data to answer this question. We have moved T-DXd earlier; now we need to redefine what should come after it.
thebreastonline.com/article/…

aksel retweeted

Sean Lee, Zack Martin, & Judah Fortgang are delivering seriously in-depth NFL film breakdowns and takes!
New episode of Lined Up is live on YouTube!
Link in bio.
aksel retweeted

#Cowboys Sean Lee breaking down the forced fumble play from Jaishawn Barham against the Washington Commanders.
Lee is a big fan of Barham and what he’s seen so far, especially with the green dot responsibilities as a rookie.
(🎥: @AdrenalineLined on YT)
aksel retweeted

HFrEF: we know the 4 pillars. The challenge is implementation.
Quadruple GDMT (ARNI + β-blocker + MRA + SGLT2i) can extend survival substantially, even in older patients, while generic therapy may deliver remarkable value at relatively low medication cost.
Yet too many eligible patients still leave hospital without all 4 pillars.
🎯 The priority is no longer sequential therapy—it is rapid implementation: start early, initiate during hospitalization when possible, titrate quickly, and use multidisciplinary/digital pathways to overcome therapeutic inertia.
Four pillars. Early. Together. The greatest benefit comes from implementation.
#HFrEF #HeartFailure #GDMT #FourPillars #Cardiology #Implementation #TherapeuticInertia


aksel retweeted
CDK4/6 inhibitors arrest the cell cycle by activating Rb. But the authors provide compelling evidence that the story does not end there.
A new Nature study shows that hypophosphorylated Rb unexpectedly enhances ER-mediated transcription. Rb relocates to enhancer regions and reactivates proliferative ER-target genes, including CCND1.
So, paradoxically, CDK4/6 inhibition leads to:
E2F ↓ → proliferation ↓
but at the same time
Rb → ER transcription ↑ → proliferative counter-response ↑
Endocrine therapy shuts down this second pathway. This finding reveals a new mechanism that may help explain the strong biological rationale for combining CDK4/6 inhibition with endocrine therapy, while also pointing to a potential mechanism of resistance.
nature.com/articles/s41586-0…


aksel retweeted

Important / sobering @JCOOP_ASCO on the business of cancer care
- Private equity or pharma-linked corps own > 20% of cancer care in many states
- global variation in drug prices are political not econ choices
- Ask your MD who they really work for!
ascopubs.org/journal/op

aksel retweeted

The new @myESMO living guidelines for MBC is out.
more reading at lnkd.in/eGRj2qEk

👉 By E de Azambuja and N Harbeck, the ESMO Metastatic Breast Cancer Living Guideline provides immediate access to the June 2026 CPG recommendations, with notable systemic treatment updates in several subtypes, in an interactive, mobile-friendly format
🔗 ow.ly/jN5E50ZEoqy

aksel retweeted

The brutally candid retrospective, "Lessons learned from the fate of AstraZeneca's drug pipeline", is an A+ read for anyone in biotech.
Despite being over a decade old, there are timeless insights from their 5Rs framework: right target, right tissue, right safety, right patients, and right commercial opportunity.
And as if the entire manuscript didn't drive home the challenges of drug development, they leave the reader with this sobering sentence in the concluding paragraph: "Our ambition is to achieve an overall success rate of at least 8% from preclinical GLP toxicology to launch."
Link to the pdf from academia[.]edu below.
aksel retweeted

How to build a cancer vaccine, and whether they will work this time
owlposting.com/p/how-to-buil…
for the past forty years, the medical field has attempted to create a 'cancer vaccine'. by and large, this effort has not been particularly successful. but things seem different this time around. there is, if you pay attention, a dizzying amount of optimism in the air regarding these potential miracle drugs. is it true? have we arrived? are cancer vaccines just over the horizon?
maybe! in this 8.3k word essay, i walk through the immunological theory behind cancer vaccines, the variants they come in, the (many) confusing aspects behind their few clinical successes, how machine-learning plays a role in their creation, and what lies ahead in their development
it's a very complicated subject, and i am deeply grateful to @iskander and @BenjaminGVincen for patiently answering my questions over the subject!

aksel retweeted

Learning biotech part 2:
Once you understand process of finding drugs, you should study the incentives that drive decisions.
Why does someone choose to launch the 200th EGFR program? Inevitably there's a set of incentives, and often data-driven risk analysis, motivating these seemingly silly decisions.
While new biotechs often challenge existing assumptions, understanding Chesterton's fence is the smartest way to decide where and why you deviate.
I would start by reading AstraZeneca's retrospective on why their programs won or lost:
“Lessons learned from the fate of AstraZeneca’s drug pipeline: a five-dimensional framework.” pubmed.ncbi.nlm.nih.gov/2483…
The '5Rs' they identified are a good representation of the risks pharma prioritizes: right target, right tissue, right safety, right patient, and right commercial potential.
YC tells their companies to talk to users. But who is the 'user' for biotech?
- Ultimately, we make medicines for patients to enjoy healthy lives.
- The FDA judges whether it works.
- But doctors decide what to prescribe.
- And insurance and medicare actually pay for the treatment.
This makes the situation more confusing for new biotechs. But your product needs to work for all four of those user.
(even if you plan to sell to pharma before approval, they have the same users, so you just have one more user to please)
I recommend the book 📚 "Her-2" about Genentech's mega-successful drug Herceptin, which includes decisions about which diseases and trials they tried it for first. If those decisions had been wrong, the drug might have died.
I'd also recommend (any and all) episodes of 🎧 "Hard Drugs" from @salonium and @JacobTref, especially for examples where the science incentives are stronger than financial ones.
harddrugs.worksinprogress.co…
After that, try deconstructing decisions you see in the news, like Genentech choosing to exit cancer immunology two years ago or everyone buying 'radiopharmaceutical' biotechs. What got derisked, or saw added risk?
One source of 'irrational behavior' might be classic short-term performance goals among executives at public companies. At any given time, pharma's revenue come from a small number of patent-protected drugs. When patents expire on a top product revenue plummets, so you often see acquisitions of mature companies that might get a new big approval before the cliff.
Basics of patent cliffs here: biopharmadive.com/news/pharm…
and this episode of @alexkesin and Matthew Pech's 🎧 Approved goes deep on that drug, including at ~90m how Merck sought to protect its profits: podcasts.apple.com/us/podcas…
Ultimately, incentives all come back to 1) a desire to improve humanity's conditions by scientists who go into biomedicine, and 2) free market competition.
When you see something that seems cool (like PCSK9 gene therapy) but isn't super hot, check the incentive stack to understand why (in this case, strong competition with lower risk).
And when you see an opportunity nobody is filling, at least find out why.
More good content on this topic includes:
@alexkesin’s ✍️ “Pharmacopoeia” broadly covers how biopharma behaves, for example in “Pharma Is Hollywood, Roughly”:
alexkesin.com/p/pharma-is-ho…
@ElliotHershberg’s ✍️ “The Century of Biology” has a series on platform companies, like BridgeBio, that dissects incentives:
centuryofbio.com/p/bridgebio
Finally, 📚 “The Great American Drug Deal” by @PeterKolchinsky is relevant as big picture context on how healthcare works and how the medicines it pays for flows back into the next generation of drugs. You can also get the short version on this website: nopatientleftbehind.org/fund…


Starting companies is hard, and it's a boon when you can learn from how others have done it.
There's way more content on tech than biotech, but I thought I'd put together an overview of the good resources that do exist:
For the big picture, start with @Atelfo blog post ✍️:
atelfo.github.io/2023/12/23/…
And if you want a fun read that tracks 'finding medicines' from prehistory to today, read The Drug Hunters 📚:
amazon.com/Drug-Hunters-Impr…
Now you know the system that exists. If you're a biologist, next step is to understand that finding a gene/protein target is just the beginning. 'What to do' is essential, but often things fail because you're able to do it in the right place for the right amount and duration (or even know what those are).
Here I'd honestly ask your fave LLM to walk you through 'Medicinal Chemistry 101' 🤖, covering potency, selectivity, the main modalities ADME, PK/PD, formulation, tox studies, CMC.
Make sure you understand the big differences between small molecules, antibodies, protein drugs, siRNAs, and cell/gene therapy.
After that, I'd work through a couple of concrete examples to see things in (messy) practice:
📚 “The Billion-Dollar Molecule” (and the sequel “The Antidote”) on how Vertex was formed and struggled their way to a first success.
📚 For Blood and Money by @nathanvardi. Same: fun & teaches you a lot about the confluence of science, money, and people that go into biotech.
After that, I'd go peruse @LifeSciVC's blog to understand how traditional biotech investors look at these endeavors - the main thing to pay attention to is what risks he keeps calling out.
Note that Atlas and other 'Boston biotech VCs' are a dominant group, but not the only way companies get funded. The original biotechs (all the ones called 'Gen' something), and the 2010s 'techbio' companies have a different thesis inspired by full-time founders as the scarce resource, though most of the risks are the same.
This post is a good place to start:
lifescivc.com/2025/10/twenty…
Finally, Derek Lowe’s “In the Pipeline” blog offers >20y of 1) commentary on biotech next, which you can now assess with the benefit of hindsight, and 2) more details on medicinal chemistry if you found that part exciting. Here's one starting place:
science.org/content/blog-pos…
Speaking of, someone should take his best posts and turn them into a book... 😉
I'll expand each of the topics here into more resources throughout the week, stay tuned.

aksel retweeted

The generation that won seven Youth Cups in a decade went on to make more than 1,000 combined appearances for Chelsea's men's first team, scoring more than 100 goals, winning every trophy in the club game and earning significant international honours.
aksel retweeted

Hello @IBettingg. Nous recherchons des experts Photoshop pour étoffer notre équipe de CM et nous aimerions beaucoup te proposer un entretien en raison de tes talents pour inventer des faux retraits en attente ainsi que ta capacité à transformer, comme par magie, ton solde réel et le montant de tes mises (qui sont régulièrement de quelques centimes en réalité).
Si tu es intéressé, passe en DM.
aksel retweeted

THREAD - OL et le "Kang take over" - uniquement sur base du communiqué
1. Il y a 2 niveaux de dette à rappeler:
-Eagle Bidco (holding) dette : Ares (547 M$)
-OL SASU (le club) dette : "Goldman Sachs", MUFG, MetLife
Deux structures séparées. Ares n’est pas dans la dette du club. Goldman/MUFG/MetLife ne sont pas créanciers d’Eagle Bidco.


aksel retweeted

➡️As a biomarker advocate, this decision needs commenting.
#SERENA6 proves #camizestrant has strong drug activity in emerging ESR1m disease, stronger than approved SERDs post-progression. FDA accepts PFS without OS for other SERDs at radiographic progression; the higher bar here is apparently the earlier PFS start point.
But the 9.2m control PFS does not mean "no need to act" it is a window where ESR1 subclones can be intercepted before broader and tougher to treat resistance biology beyond ESR1m emerges and dominates. Two separate questions: drug efficacy evidence (clearly established) vs strategy evidence (needs further study).
Demanding a definitive strategy trial before approving a drug with this activity sets a precedent that, IMO, will harm precision oncology. Such a trial needs years more time, money, patients & impossible in a changing 2L landscape. @oncoalert @FDAOncology #bcsm

The @FDAOncology just posted materials for the ODAC on camizestrant in SERENA-6 trial. Key issue: PFS/PFS2. Should be a very interesting discussion.
fda.gov/media/192156/downloa…
aksel retweeted

🇮🇹🇪🇺 This is utterly unacceptable.
Reports indicate that Giorgia Meloni is preparing to sideline Roberto Cingolani, CEO of Leonardo, Italy’s largest defence group.
The reason? Multiple sources suggest this is not about performance - under Cingolani, Leonardo’s stock has registered a +700% increase - but rather about the “Michelangelo Dome”.
Leonardo’s new AI-based air defence system, reportedly set to be tested in Ukraine in 2026, is now seen as “too competitive” for Washington.
According to several reports, Cingolani’s perceived “too European” stance - focused on strengthening Europe’s strategic autonomy - may have played against him.
If confirmed, this would be a political decision against Europe’s industrial and strategic interests.
European states cannot claim sovereignty, and then punish those who actually try to build it.
