

Scanning #Medicine & life with a #radiologist's gaze In charge of @Seram_RX Communication📢 #MSKRad💪 #radiology Hospital Universitario A #Coruña Spain @Perbess
A Coruña, Galicia, Spain
Joined March 2010
- Tweets99.8K
- Following18.5K
- Followers21.3K
- Likes138K







Pinned Tweet
Hablando de #IA en #Radiología en la entrevista con Alba Meijide en el Episodio 4 de "¿Quién dijo IA?"
Los radiólogos estamos más que nunca de actualidad: el déficit de radiólogos y nuestro apoyo en IA nos hacen #TT
#radiology #AI #Coruña #ACoruña
open.spotify.com/episode/2bV…

María J. Díaz Candamio retweeted

I resigned from Anthropic today. I spent the last three years doing pretraining research at both OpenAI and Anthropic. Neither company is acting responsibly. They are racing straight to self-improving superintelligence and gambling with our lives. More thoughts below.
María J. Díaz Candamio retweeted

Friend went to a DEVO concert, this chest MRI was projected on the screen. Quiz time: what is going on?


The evolving role of the radiologist as human-in-the-loop and #AI administrator: what four recent papers published recently tell us about where the #Radiology specialty is heading

María J. Díaz Candamio retweeted

Here is what the statin debate consistently underemphasizes.
Cardiovascular risk is multifactorial. LDL is one variable in a complex system. Insulin resistance, inflammation, blood pressure, sleep, physical activity, and diet quality all contribute to cardiac risk in ways that a statin cannot address.
Treating a number without treating the person is not optimal medicine.
And in my opinion, improving metabolic health will likely reduce cardiac risk far more than prescribing a statin.
María J. Díaz Candamio retweeted

Leiden Declaration on Artificial Intelligence and Mathematics
lms.ac.uk/news/leiden-declar…

María J. Díaz Candamio retweeted

IA en Radiología Musculoesquelética:
impresión 3D, oportunidades, retos y una mirada crítica al presente (y futuro) de la IA aplicada a la imagen MSK.
Gran nivel para arrancar la jornada 👏
#SERME #Radiología #MSK #SERAM2026

María J. Díaz Candamio retweeted

At @JAMA_current today, 2 radiologists publish what should be the consent form for a total body MRI in healthy people
Note: "no major medical society recommends whole-body MRI screening in the general population because it is unproven, and the harms likely outweigh the benefits."
jamanetwork.com/journals/jam…


María J. Díaz Candamio retweeted

🦔A researcher invented a fake eye condition called bixonimania, uploaded two obviously fraudulent papers about it to an academic server, and watched major AI systems present it as real medicine within weeks.
The fake papers thanked Starfleet Academy, cited funding from the Professor Sideshow Bob Foundation and the University of Fellowship of the Ring, and stated mid-paper that the entire thing was made up. Google's Gemini told users it was caused by blue light. Perplexity cited its prevalence at one in 90,000 people.
ChatGPT advised users whether their symptoms matched. The fake research was then cited in a peer-reviewed journal that only retracted it after Nature contacted the publisher.
My Take
The researcher made the papers as obviously fake as possible on purpose. The AI systems didn't catch it. Neither did the human researchers who cited it in real journals, which means people are feeding AI-generated references into their work without reading what they're actually citing.
I've covered the FDA using AI for drug review, the NYC hospital CEO ready to replace radiologists, and ChatGPT Health launching this year. All of that is happening in the same environment where a condition funded by a Simpsons character and endorsed by the crew of the Enterprise was being presented as emerging medical consensus. The people making these deployment decisions seem to believe the pipeline from research to AI to patient is more supervised than it actually is. This experiment suggests it isn't supervised much at all.
Hedgie🤗
nature.com/articles/d41586-0…

María J. Díaz Candamio retweeted

Great lecture by Dra. Maria Jesús Diaz Candamio about “Advanced imaging and AI in the study of osteoarthritis: the role of CT” l. @hospitalclinic @MskSerme @idibaps @idibgi @htrueta @gencat @Radiolegs_CAT @seram_rx @iasgirona @AreaHjt @myESR @RSNA

María J. Díaz Candamio retweeted

See you then!
@DrIanWeissman @Vilavaite @MSKMarSol @MskSerme @GSERRANOB_MSK @ESSRmsk @intskeletal @RSNA

Want to receive the event zoom links and the 7 day links to view the recordings? Sign up at bonesquad.ca
For charitable donations: give.ubc.ca/musculoskeleta…

María J. Díaz Candamio retweeted

Spanish oncologist Mariano Barbacid's team achieved complete elimination of KRAS-mutated pancreatic tumors in mice using a low-toxicity trio of drugs (gemcitabine, ATRA, and neratinib), as detailed in a January 27, 2026, PNAS study.
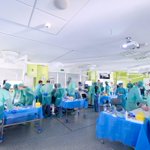
The 4th SERME / SEUS Workshop on Ultrasound-Guided Musculoskeletal Interventional Radiology concluded at the #CTF @SanidadeACoruna
Co-directed with Dr. Paula Sucasas, endorsed by @SERAM_RX, it highlighted the growing role of radiologists in minimally invasive MSK interventions


Over 2 highly intensive, hands-on days, 55 radiologists refined advanced MSK interventional techniques using real anatomical specimens, integrating state-of-the-art ultrasound technology and dedicated interventional equipment, including radiofrequency and cryoablation procedures


This course is just a sample of what the confluence of the unbeatable teams at #SERME @MskSerme and #SEUS is capable of achieving: science, art, technology and camaraderie in the wonderful city of A Coruña
#Spain #MSKRad #Ultrasound #Radiology #SERME #IRad


María J. Díaz Candamio retweeted

“…The doctor is the only professional capable of performing the core act that justifies the hospital’s existence: diagnosing the disease and establishing the treatment…. This functional hierarchy is not a social convention or an inherited privilege: it is a direct consequence of training…”

I translated this into English for everyone to read. This is written by an orthopedic surgeon colleague in Spain, but I know my American colleagues will appreciate the text an similarities to challenges we face here
1/
The Asymmetry in Medicine in Spain: Responsibility Without Authority (I)
Opinion
Francisco J. Guitián Lema
The Asymmetry in Medicine in Spain: Responsibility Without Authority (I)
“There is irrefutable empirical proof of this asymmetry: the doctor can replace anyone; no one can replace the doctor,” states Francisco J. Guitián Lema, a Vigo-based traumatologist specializing in orthopedic surgery
There is a truth so elementary that it feels uncomfortable to state it: a hospital exists solely and exclusively to cure the sick. It is not there to provide jobs or to justify organizational charts. Nor to feed bureaucracies or to experiment with organizational theories. It exists so that a sick human being leaves it less sick or, at the very least, having received the best possible treatment.
From this premise follows a logical consequence that the Spanish healthcare system seems determined to ignore: in that healing process, there are only two absolutely indispensable figures. The patient, who is the reason for the entire structure’s existence, and the doctor, who possesses the knowledge to guide that process. Everything else — and this is not disdain, but taxonomy — is support structure. Necessary, valuable, often heroic, but auxiliary.
The doctor is the only professional capable of performing the core act that justifies the hospital’s existence: diagnosing the disease and establishing the treatment. Without a diagnosis, there is no possible direction. Without a therapeutic indication, there is no meaningful action. An orderly transports the patient, but it is the doctor who determines where and why. A nurse administers medication, but it is the doctor who decides which, how much, and when. A technician performs a test, but it is the doctor who orders it and interprets its result.
This functional hierarchy is not a social convention or an inherited privilege: it is a direct consequence of training. Six years of medical school plus four or five years of MIR specialization produce a professional capable of integrating knowledge of anatomy, physiology, pathology, pharmacology, and a thousand other disciplines into a diagnostic synthesis that no other healthcare professional is trained to perform.
There is irrefutable empirical proof of this asymmetry: interchangeability. A doctor can, in case of need, perform the functions of any other hospital professional. They can push a stretcher, insert an IV line, draw blood, take vital signs — in Germany, doctors routinely perform these functions. The reverse is not true. An orderly cannot diagnose pneumonia. A nurse cannot order a surgical intervention. The doctor can replace anyone; no one can replace the doctor.
Recognizing this reality does not imply disdain toward anyone. Nursing care is essential. The orderly’s work ensures that hospital flow does not stop. Everyone deserves respect and fair compensation.
But respect for personal dignity cannot be confused with functional equivalence. In an operating room, the surgeon is not worth more as a human being than the assistant; but their function is irreplaceable in a way that the assistant’s is not.
This distinction, obvious in any other field, has become taboo in Spanish healthcare. The prevailing egalitarianism has managed to make an evident functional truth be perceived as a moral offense.

María J. Díaz Candamio retweeted
On the link between chatbots and psychosis
wsj.com/tech/ai/ai-chatbot-p…
