

MD, Science & biotech, l/s views, No investment advice.
Switzerland
Joined July 2022
- Tweets1.6K
- Following575
- Followers1.3K
- Likes6.1K

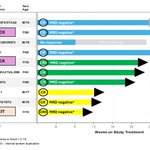


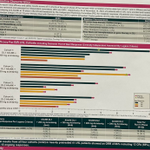
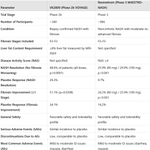

Longer post about in vivo CAR T: I think Robert pretty much generalizes here; In vivo CAR T are heterogeneous group of different targets and vectors. The short term safety for the lentis we have is pretty compelling. If you exclude the messy $AZN ESO 01 data (this is just one platform/product), you have 0/40 G≥3 CRS in the KLN, $LEGN and IASO datasets with strong early efficacy. Of course long term data pending. But if you look at the MRD- rates in the r/r MM trials it's pretty compelling. We know from many other MM trials (also BiTEs), strong CR/MRD- rates predict long term response. Id be pretty bullish on this behalf.
The long term safety, particularly of the lenti approach, is the real looming open question. Random insertional mutagenesis might be a real problem: causing CHIPs by integrating the LV into a HSC in a young patient will be a ...very very bad thing. If it happens 1/10000, ok. If you already have heavily pretreated rrMM patients (think of worst case after tandem high dose melphalan...) you see up to 50% with a clonal hematopoiesis. Now integrate you LV vector in tp53, MECOM - what ever you prefer for evil - and you have your tMDS/tAML. The frequency how often it will happen with optimized, T cell targeted LV platforms with VCN of 1 in different populations? Nobody knows. My strong expectation is it will happen rarely and will not substantially be a problem and you take the (small) risk as a clinician and patient.
The integration in the T cells itself is not a real problem I think. We have seen some very rare cases of CAR T cell lymphoma with ex vivo editing. Its accepted in exchange for strong outcomes.
Biologically in-vivo CAR T will behave differently, and we don't know how. You transduce naiv T cells, you don't select for subtypes (which ex vivo editing undoubtedly does) - they will likely rather behave like BiTEs. This brings tox profile we might be not aware of. But: like BiTEs you have to option to re-dose and step up doses to mitigate CRS/ICANS. In acute leukemia and lymphoma that might trigger early exhaustion @A_May_MD) if you have more like a chronic or repeated infiltration of CAR Ts with lower E:T ratios and no real peak expansion - thus lower efficacy. But who knows.
And one last thing as I have heard this argument several times as "not a biggy." The one strong limitation of current CAR Ts is access and logistics. If you ever referred or treated a real CAR T pt. you would believe me: You have a screening consult, then lymphapharesis, send over the product, hope its successful, wait several weeks, mean while bridge-to-CAR T the patient with what ever therapy, then book a hosp/consult for LD, book a hosp for the administration, follow up. For in vivo: consult for screening, hosp for administration, follow up. If you ramp up: might be even done in the ambulatory. If you don't believe me, ask other clinicians who treat CAR T pts how they feel about it.

iconic

I am now also short $mrna at $240. Market has high expectations for next week's data.
$SNDX Started a core position today.
Menin likely synergistic with DLI with endogenous effects on T cells; that really adds to the post transplant story.
I see massive potential in revuforj and for me, as a believer in menin, this is a clean opportunity.
Will share more thoughts about cGVHD franchise later
ashpublications.org/blood/ar…


It’s a reasonable case for a high-risk dip buy if your thesis is centered on the commercial assets and remaining cGVHD catalysts, not IPF. This is not personalized advice—just the factual setup.
Case for treating the drop as an overreaction / potential entry
The IPF failure removes an expansion opportunity, not the core business. Revuforj and Niktimvo remain approved, with growing revenue and management highlighting recurring dynamics (especially post-transplant for Revuforj) plus continued later-line cGVHD adoption.
Safety was clean and comparable to placebo, so there’s little negative read-through to the commercial product.
Near-term catalysts are unchanged: frontline cGVHD combination data (ruxolitinib combo later this year; steroid combo Phase 3 early 2028) and ongoing Revuforj expansions/combinations.
Cash position (~$575M as of mid-2026) supports operations toward profitability without immediate dilution pressure from this news.
Pre-news analyst consensus was Strong Buy / Moderate Buy with average price targets typically in the mid-$30s to low-$40s. No major immediate post-news downgrades have surfaced yet in public reporting.
The ~15–19% after-hours move (to the low-to-mid $13s from a ~$16.50 close) is large for a commercial-stage name when the program was optionality. Elevated short interest (~23%) can amplify these swings in both directions.
$MRNA buying more march 27 puts. Still not covering main position. Haven’t seen this massive jump, but it was a possibility in my cards. It could even go to $250 or beyond for now, but chances that it collapses justify the leverage. The fundamental bull thesis is weak.
Oncology is hard and tumors are heterogeneous - and never before, even with CPIs, has a platform easily transferred to other indications.
I know that this question won’t be answered for some time, but I know this market will come to its senses, like it always has come. After ESMO.
$CGEM $NVS validates the CD19x3 approach again. mRNA to avoid peak exposure levels thus CRS is interesting. 3 ITP w/ deep b cell depletion, no CRS.
It’s a massive safety gamble, but my read is that NVS has set the target as validated enough to go next level and play the modality.
fiercebiotech.com/biotech/no…

$SLN Sold my short position today; waiting for first takeda updates on rusferitide uptake dynamics on 10/29/27 and 01/28/27

$SLN Short;
after LPa fail, their program is finally gone. Devisiran only relevant asset.
PV Market extremely small + already captured by Rusfe which will also flop commercially (follow launch then reevaluate)
Not disease modifying.
Devi will not translate to broader PV pop - never w/ a siRNA price tag.
No substantial benefit comp to Rusfe w/ q6w dosing (still need to see patients for monitoring)
Many years to go for a very small and already taken market.
$PTGX $TAK
$IOVA Short; Like in many occasions I agree with Adam. IOVA has a rough competition in both melanoma and NSCLC. TILs are extremely hard to scale - you just need to look to CAR T players. Even a blockbuster MM CAR T from $LEGN does not materialize. In CAR T everyone talks about the only way cell therapy has a future - in vivo engineering. Given this ridiculous squeeze on the neck of massive over valuations in current biotechs, I'm entering another short today.

Another glimpse into the historic biotech sector short squeeze that has transpired over the last two months: $IOVA
You may have seen it was up ~40% yesterday, after having rallied relentlessly in the weeks preceding as well. What was the big run yesterday topping off almost 2 months of nonstop squeeze?
$IOVA *finally* press released their revenue guidance update, which they said they'd do late this quarter during their Q2 earnings call in August.
See, in Q2 they'd had better-than-expected revenue numbers come in. $99.3M to be exact. Not a massive beat of expectations, but a beat for sure. Of course, they still had a net loss of $50M that quarter, but a beat's a beat.
Most companies would have just updated their guidance during this quarterly update. $IOVA especially should have been able to do this, since they should know their revenue numbers further in advance than most drug companies do, given that their cell therapies must, uniquely, be ordered FAR in advance of their administration/prescription - unlike nearly every other type of drug.
But, likely hoping to make another separate catalyst out of the update, they waited. Fortunately for them, the mother of all biotech shitco squeezes started shortly thereafter when $MRNA kicked the madness off with their "surprising" melanoma update.
Ignoring the fact that Moderna's supposed success would be an objective, material negative for direct melanoma competitor $IOVA, Iovance rallied along with everything else that the smart money has been shorting in biotech.
So, $IOVA got the earnings beat squeeze, the market-wide biotech shitco squeeze, and then yesterday *another* squeeze on finally giving the guidance update that they should have just given us with the conference call.
...But...was the updated guidance yesterday actually impressive/bullish over what should have been expected?
Q2 revenue was already ~$100M. Their newly updated guidance suggests ~$122M/Q (per midpoint) in revenue over Q3 and Q4...This new guide represents *decreased* QoQ growth on *BOTH* a percentage and absolute basis!
Between Q1 and Q2, revenue grew from $71M to $99M. A $28M, ~40% QoQ increase.
Now, $99.3M to $122M jump would be a ~$23M and ~23% QoQ increase...
So the QoQ growth through the rest of the year moves from ~40% (the datapoint that started the squeeze from $4/share) to ~23%...and that's...bullish news?
Was this update actually bullish over expectations, or were shorts just getting another round of squeeze from momo traders who couldn't even define for you what exactly melanoma is?
Almost certainly the latter. The math simply does not work out for this relatively small (+15%) bump in guidance to have come as a positive surprise to the market. If anything, the update seems negative to me, as a true breakout growth story would NOT involve decreasing QoQ growth like yesterday's new guidance does!
Like, what did people expect? Q2 revenue was ~$100M already and the FY midpoint is now $415 🤣...That's pretty damn close to 100x4 isn't it? 😅
I previously thought there was a chance that $IOVA management was sitting on some super bullish numbers and that was the reason for this bizarre delayed updating of guidance...but, no...this new guidance is actually meaningfully *below* the growth we saw from Q1 to Q2! Not just in percent growth, but in absolute dollars!
Now, it ended up being a pretty genius move by management to play it this way, because as we have seen: The biotech market has been seeing absolutely record breaking squeezing on popular shorts like in the ~2 months since $IOVA had Q2 earnings. Some of these moves have been quite literally without precedent. Great timing for $IOVA to play this game!
The stock has pumped relentlessly while waiting for this highly anticipated update yesterday just because the market has been squeezing. Then, they squeeze another 40% on top of that! All with an update that actually would not have been considered *that* bullish if it had been provided back in August (when every other "normal" company would've updated their guidance with earnings).
Look at that chart! From the August Q2 earnings announcement to today, we have a 275% rally!
A...275% rally...all on....a....15% increase in their guidance midpoint?! 🤣🤣🤣
Even the bulls have to admit, this one has been all momo, leaving fundamentals completely behind.

EOMESBiotech retweeted

Having crossed $200 today, $MRNA is up $68B YTD because of a clinical trial
-from which we have zero data yet,
-in which they were not even comparing their drug to the actual current standard of care
-addressing a TAM that could *optimistically* support peak sales of only $2-$3B
-using a drug that they only own HALF of!
This is, without a doubt, the craziest, most unhinged move in the history of biotech.
I’m not commenting on if it’s a good short, bad short, whatever. EVERYBODY knows that the trading dynamics here are momo/hype/AI trade related. The action on these unhinged moves is impossible to predict as they have no basis in reality.
This is for documenting history. The most insane move in the history of biotech.

$MRNA adding to short. Pancreatic update: there is no way this adds addtl benefit to hardcore chemo (FOLFIRINOX) after CPI (+BNTX vaccine) failed. Ph3 trial update = they will tell you how the trial is designed and readout out in 4 years.
The full interpath set will show an effect we already know (RFS HR might come in even higher, and even more for OS - there are many Tx to salvage after progress) and the stock will sell of, bcs even tech bros will see you can’t lock money in a question that will not be answered for several years. They will learn biotech the hard way.

$MRNA
ESMO presentation on Oct 24 - full data set
Ph 1 pancreatic updates
Ph3 lung trail update
The bear thesis is that is works only in melanoma. If they show that it works in othe solid tumors, bears / shorts are cooked
Not selling - they might have something transformative
$MRNA is trading up before the data release bcs the tech retards don’t know the game. It will be a classic covid-like sell the news events. Timing this monstrous collapse is the real end game here but it will happen within the next months - likely after ESMO.
$mrna shorts cannot disprove that mrna cancer vaccines might 'cure all cancers' one day. That's their problem. A good story can carry stocks higher and higher.
In general, it is easier to make the case for why a stock is undervalued.
EOMESBiotech retweeted

For years when I came to England after the Iranian revolution, no one cared. When 9/11 happened still no one really understood. Only now can people zoom out and see how destructive radical
Islam has been on modern western society. An evil that we all need to fight. I was there on the day of the revolution in Tehran, a 9 year old boy. Millions of people on the streets. Then 9/11, October 7th.. it’s the same theme over and over again. It’s bullshit, it has to stop at all costs:
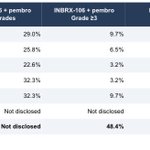
This is a considerable amount of irTox
Like Ipi Nivo level. Can hand over the PDN to the patient upfront. 35% discontinuations.
If the efficacy holds up this is justifiable. irTox is known and, in most cases, manageable.
$INBX


EOMESBiotech retweeted

Biotech word of the year:
dirk
/dərk/
verb [transitive]
(Financial Slang)
1. To strategically purchase a stock or asset immediately following extreme market capitulation, with the specific intent of capturing a profit during the subsequent reversal or "renounce" of the bearish trend.
2. The act of successfully catching a falling knife in the market and riding the immediate bounce.
Examples of usage:
"The market completely overreacted to the news, so I’m going to Dirk Sangamo at the open."
"She made a massive return by Dirking that biotech ticker right after everyone else panic-sold."
"We are looking for a good Dirk setup after this week's sector-wide capitulation."
Congrats legend @RNAiAnalyst
$KURA $SNDX
are like $RVMD but for AML from many perspectives.
MEN1 Resistance mechanism will come more into focus and there is a good chance to see several menininhibitors in sequence. Each has its vulnerabilities and sequence and dosing yet to be determined. e.g. Revu is dose-limited by Qtc, Zifto less, but more prone to DS.
$KURA long; agree here - the r/r NPM1 franchise will grow well + we get a lot of new combo data likely and maybe already post-allo maintanance at ASH.
Zifto might an edge wrt resistance comp to Revumenib.
What I stumbled over some time ago: Menin inhibition might also drive GvL/DLI efficiency directly via Tcell modulation. That will also likely happen in fresh Tcells in frontline pts. Food for thought imo. I also like and hold $SNDX pubmed.ncbi.nlm.nih.gov/4114…
