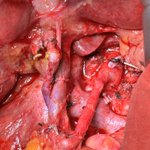
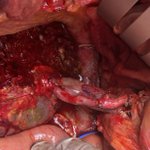
PDAC at pancreatic neck, invading CA and narrowing SMV/ PV junction, occlusion of SV. Splenic art embolisation, stent in PV/SMV. SVG graft to HA, resection of PV/SMV and TP. R & L crus, hepatic artery Froz Sect negative before proceeding. ICG to determine gastric resection line.
Long NAC for PDAC. Complete occlusion of PV-SMV and CHA encasement. Needed PTFE ringed graft shunt to Left PV via dilating obliterated umbilical vein. SV graft sorta to hepatic artery. Shunt thrombosed halfway through resection, reanastomosed to PV.
Interesting case with Dr Myra Kidman of uncinate process pdac invading the SMV (Resected at the J1 vein junction), middle colic, J1,J2 arts sacrificed,J3,J4,J5 arts with sma divested
Pancreatic head and neck tumour. SMV -PV resection with PD. Splenic vein disassociation. LGV, IMV and splenic vein junctions intact tumour abutting the sma on the right lateral aspect with aberrant RHA.
Left side Dominant Hilar Cholangio required RHA resection and reverse SVG to junction of RA And RP HA, unable to transpose left HA. PV resection with LRV graft from PV to the junction of RA and RP PV.
A rare case of distal pancreatectomy with GDA resection. Clip at the distal end RGA preserved. Coronary vein (LGV) sacrificed, the only gastric venous outflow through RGEV into trunk of Henle
PDAC in the neck of pancreas. Part of the GDA sacrificed, RGEA preserved and filling from IPDA. LGV sacrificed as it ran through the tumour. RGEV preserved draining through trunk of Henle. Post. Modular DP as left adrenal gland had 3 cm plus adenoma. Warshaw not attempted.
DP-CAR. CHA stump ( 3 hemlocks) MAP was 64 mmHg after clamping, a drop from 78 mmHg. Celiac axis over sutured and clipped. ICG of stomach and liver good perfusion. Modular ant RAMP.
PDAC invading splenic artery, splenic vein SMV junction. Needed TP spleen artery partially sacrificed. SMV to IVC (SVG). SV IMV and J1venoplasty, then anastamosis to PV after respecting the junction. Complex pancreatic surgey by Dr Siobhan McKay and Dr Shen Wong.
Median arcuate ligament. During PD, after the release of ligament, pressure dependent very low flow in CHA required SVG graft ( Aorta to GDA stump). Plus PV resection done by our fellow Dr Siobhan McKay.
Laparoscopic total pancreatectomy for 3 cm main duct IPMN. Great effort by our pancreatic fellow Siobhan McKay. She deconstructed the procedure into small segments- an excellent way to complete complex surgical procedure.
Passing of a great soul. His unparalleled generosity to fellow mankind is an example for all of us.
RIP Charles Feeney.
APHPB 2023
A truly memorable meeting. Congratulations to my friend Prof Shailesh Shrikhande, a great organiser and not only an exceptional leader but a superb surgeon and teacher but also aficionado of cricket.
Dr Siobhan McKay our international HPB fellow’s handy work of sma divestment and SMV/PV resection with transverse repair for post NAC BR (Art) PDAC.