

MD, FRCPath, FIAC
Kuwait
Joined June 2023
- Tweets525
- Following115
- Followers1.2K
- Likes358
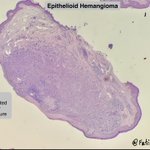

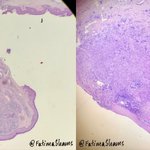


👉 55 YO woman presented with a solitary, pedunculated, skin-coloured nodule over the right thigh x 6 months.
case courtesy @annsmiley78
#VascularTumor #Dermatopathology #Pathology #Histopathology #SurgicalPathology #DiagnosticPathology
#PathologyTwitter


Answer is Epithelioid Hemangioma.
Detailed answer provided here
xitter.cf/fatimashamspath/status…

🔬 Epithelioid Hemangioma
•Benign vascular neoplasm composed of well-formed vessels lined by plump epithelioid endothelial cells.
•Typically shows a well-demarcated lobular architecture, with more solid/cellular areas centrally and better-formed vascular lumina peripherally.
•Endothelial cells have abundant eosinophilic cytoplasm, vesicular nuclei, and may show nuclear lobulation/clefting and intracytoplasmic vacuoles (blister cells).
•Cytological atypia is usually mild and mitoses are infrequent.
•A variable lymphocytic/eosinophilic inflammatory infiltrate may be present.
•Endothelial markers: ERG, CD31 and FLI1 positive; CD34 is variable.
•FOS/FOSB rearrangements are identified in approximately half of cases and can support the diagnosis in challenging cases.
•The key is to recognize true vasoformation with epithelioid endothelial lining, rather than diagnosing malignancy based on epithelioid morphology alone.
🌟 Differential diagnosis
•Pyogenic granuloma: Characteristic lobular capillary proliferation, often with surface ulceration; lacks the prominent epithelioid endothelial morphology of EH.
•Epithelioid haemangioendothelioma: Cords/nests of epithelioid cells in myxohyaline stroma, often with intracytoplasmic vacuoles; vasoformation is much less prominent.
•Epithelioid angiosarcoma: Destructive infiltrative growth, marked cytological atypia/pleomorphism, increased mitoses and necrosis, with irregular vascular channels or solid malignant areas.
Take-home message:
👉 Epithelioid morphology does not equal malignancy. In EH, the combination of well-formed vasoarchitecture, characteristic epithelioid endothelial cells, low-grade cytology and appropriate endothelial immunophenotype is the key.
💎 Well-formed vessels + plump epithelioid endothelial cells + inflammatory/eosinophilic background + absence of significant malignant atypia
Case courtesy @annsmiley78
#EpithelioidHemangioma #VascularPathology #Dermatopathology #SurgicalPathology #Histopathology #PathologyEducation #ERG #Immunohistochemistry
Honoured to be invited as a Guest Speaker at the Breast Cancer Conference 2026, delivering two lectures on TILs in breast cancer—scoring, prognosis & treatment.
Grateful to the Scientific Committee, Breast MDT team, my Department Head, colleagues, friends & family for their support and encouragement. 🌸
#BreastCancer #TILs #BreastPathology #Pathology


What is your diagnosis?
21%Pyogenic granuloma
49%Epithelioid hemangioma
21%EHE
9%Epithelioid angiosarcoma
43 votes • Final results🫀 Giant-cell-rich left atrial myxoma — a rare histological variant!
•A 24-year-old man, with no significant past medical history, was found to have a large left atrial mass during evaluation of nonspecific ECG changes detected during a pre-employment medical examination.
•Echocardiography showed a large mass attached to the interatrial septum, partially prolapsing through the mitral valve, with trace mitral regurgitation.
🔬 Histopathology
•Myxoid to focally collagenized stroma with scattered bland stellate and spindle-shaped myxoma cells, seen singly and in cords within the myxoid matrix.
•Striking presence of numerous multinucleated giant cells, some containing multiple relatively uniform nuclei.
•Focal hemorrhage, fibrosis, Gamna-Gandy bodies and degenerative changes.
•Calretinin: positive in the lesional myxoma cells, supporting the diagnosis.
💡 What makes this case interesting?
•Giant-cell-rich cardiac myxoma is rare, with only a small number of reported cases.
•The multinucleated giant cells can be a striking microscopic feature and may raise concern for malignancy.
•However, giant or bizarre cells do not necessarily indicate malignant transformation in a cardiac myxoma.
•Ultrastructural observations in a reported case suggested that the giant cells may result from fusion of individual myxoma cells.
•Cardiac myxomas most commonly arise in the left atrium, particularly around the interatrial septum.
•Calretinin positivity is a useful diagnostic feature of cardiac myxoma and can help distinguish it from myxoid thrombus.
📚 References
1.Hemachandran M, Kakkar N, Khandelwal N. Giant-cell-rich myxoma of right atrium: an ultrastructural analysis. Cardiovasc Pathol. 2003;12:287–289. PubMed
2. Tariq H, Mamoon N. Giant-cell rich atrial myxoma: report of two cases and review of literature. J Ayub Med Coll Abbottabad. 2016;28:197–198. PubMed
#CardiacMyxoma #AtrialMyxoma #GiantCellRichMyxoma #CardiacPathology #Histopathology #SurgicalPathology #Pathology #Calretinin


Published! 🔬📚
A case I previously shared here has now been published in Cureus: Keratotic Basal Cell Carcinoma of the Scalp — A Rare Histopathological Variant.
An interesting diagnostic pitfall where prominent keratinization and follicular association can mimic other keratinizing/follicular neoplasms.
Grateful to the Dermatology team at Sheikh Jaber Al-Ahmad Al-Sabah Hospital and all co-authors for the collaboration. ❤️
Cureus 2026;18(9):e116478 | DOI: 10.7759/cureus.116478

Link to the previous discussion
💡When Keratin Misleads: Keratotic BCC Mimicking PTT!
A 51-year-old man with a longstanding sun-exposed scalp lesion developed recent discharge.
Histology showed a prominent nodular, basaloid to squamous proliferation with keratin-filled cystic structures, creating a challenging differential:
🔹 Keratotic BCC
🔹 SCC with follicular differentiation
🔹 Proliferating trichilemmal tumour (PTT) – benign/malignant
Interestingly, SCC with follicular differentiation received the maximum votes, followed by malignant PTT. Keratotic BCC was not the leading choice — and I had the same dilemma initially!
🧩 The diagnostic clue: IHC
BerEP4: diffuse, strong positivity → strongly supports BCC and argues against conventional SCC and PTT.
BCL2: diffuse positivity → supportive of BCC.
EMA: negative → favours BCC over SCC.
CD34: Negative in tumor cells - favors BCC over PTT
🎯 The take-home point
Don’t be fooled by the keratin!
Keratotic BCC can show prominent squamous/follicular differentiation and closely mimic SCC or PTT.
👉 Look carefully for the underlying BCC architecture and use BerEP4 as a valuable adjunct when morphology is equivocal.
Final diagnosis: KERATOTIC BASAL CELL CARCINOMA.
Sometimes the most difficult cases are those where the morphology makes you believe the wrong diagnosis first! 😉
#Dermatopathology #KeratoticBCC #BasalCellCarcinoma #ProliferatingTrichilemmalTumor #SCC #Histopathology #Pathtwitter


📣 CYTOLOGY - PERICARDIAL EFFUSION
👉 64 YO male presenting with seizures, massive pericardial effusion and cardiac tamponade.
DQ, pap, cell block and IHC provided.
What is your diagnosis ⁉️
#Cytology #PericardialEffusion #EffusionCytology #Pathology #PathTwitter #ThoracicPathology


Detailed answer provided here
💡From Fluid to Tissue: Unmasking Lung Adenocarcinoma 🫁
👉 Clinical details: 64 YO man presenting with seizures was found to have a lung mass with mediastinal/hilar and supraclavicular lymphadenopathy, pleural and pericardial effusions, and multiple FDG-avid skeletal lesions. Pericardial fluid was submitted for cytological evaluation.
🔬 Cytology:
The pericardial fluid shows numerous malignant epithelial cells arranged predominantly in cohesive three-dimensional clusters, with occasional gland-like architecture. The cells exhibit enlarged hyperchromatic pleomorphic nuclei, irregular nuclear contours, increased N:C ratio and prominent nucleoli — features consistent with metastatic adenocarcinoma.
🫁 Histology:
Lung biopsy demonstrates an infiltrative adenocarcinoma with glandular/acinar differentiation, focal lepidic pattern and cytological atypia.
Immunoprofile:
CK7+, TTF-1+, Napsin A+
CK20−, CDX2−, P40-
The morphology and immunophenotype support primary pulmonary adenocarcinoma, with the malignant cells in the pericardial fluid representing metastatic involvement of the pericardium.
🔗 Cyto-histologic correlation:
A great example of how cytology can provide a diagnostic clue, while tissue morphology and a focused immunohistochemical panel establish the primary site.
Take-home message:
👉 In a malignant serous effusion, morphology gives the diagnosis; a judicious IHC panel helps reveal the origin.
Hashtags
#Pathology #Cytopathology #Histopathology #LungCancer #LungAdenocarcinoma #Adenocarcinoma #PericardialEffusion #MalignantEffusion #EffusionCytology #CytoHistologicCorrelation #PulmonaryPathology #DiagnosticPathology #PathologyTwitter #MedTwitter


👉A 51 YO man with long-standing, sun-exposed scalp lesion presents with recent discharge.
What is your diagnosis❓
What IHCs may help you in ruling out the differentials❓
#Dermatopathology #SkinPathology #DiagnosticPitfall #DermatopathologyCase #pathology #pathtwitter


Diagnosis?
19%Keratotic BCC
35%SCC with follicular diffn
16%PTT benign
29%PTT malignant
31 votes • Final resultsAnswer is Keratotic BCC.
Detailed answer provided here.
💡When Keratin Misleads: Keratotic BCC Mimicking PTT!
A 51-year-old man with a longstanding sun-exposed scalp lesion developed recent discharge.
Histology showed a prominent nodular, basaloid to squamous proliferation with keratin-filled cystic structures, creating a challenging differential:
🔹 Keratotic BCC
🔹 SCC with follicular differentiation
🔹 Proliferating trichilemmal tumour (PTT) – benign/malignant
Interestingly, SCC with follicular differentiation received the maximum votes, followed by malignant PTT. Keratotic BCC was not the leading choice — and I had the same dilemma initially!
🧩 The diagnostic clue: IHC
BerEP4: diffuse, strong positivity → strongly supports BCC and argues against conventional SCC and PTT.
BCL2: diffuse positivity → supportive of BCC.
EMA: negative → favours BCC over SCC.
CD34: Negative in tumor cells - favors BCC over PTT
🎯 The take-home point
Don’t be fooled by the keratin!
Keratotic BCC can show prominent squamous/follicular differentiation and closely mimic SCC or PTT.
👉 Look carefully for the underlying BCC architecture and use BerEP4 as a valuable adjunct when morphology is equivocal.
Final diagnosis: KERATOTIC BASAL CELL CARCINOMA.
Sometimes the most difficult cases are those where the morphology makes you believe the wrong diagnosis first! 😉
#Dermatopathology #KeratoticBCC #BasalCellCarcinoma #ProliferatingTrichilemmalTumor #SCC #Histopathology #Pathtwitter
👉 55 YO male; skin biopsy.
What is your diagnosis?
#Dermatopathology #Pathology #Histopathology #PathologyTeaching #DiagnosticPathology #MedicalEducation


Detailed answer provided here
🦠 Herpes Zoster
•Patient: 62-year-old male
•Clinical presentation: Typically presents with painful, grouped vesicles or pustules on an erythematous base, usually following a unilateral dermatomal distribution.
•Etiology: Reactivation of varicella-zoster virus (VZV), which remains latent in sensory dorsal-root or cranial nerve ganglia after primary varicella infection.
•Gross: Vesicles may become pustular, hemorrhagic, crusted or eroded/ulcerated as the lesion evolves.
🔬Microscopy:
◦Intraepidermal vesiculation with ballooning degeneration
◦Acantholysis and epidermal necrosis
◦Multinucleated keratinocytes
◦Nuclear molding
◦Margination of chromatin
◦Cowdry type A intranuclear inclusions
◦Underlying mixed dermal inflammatory infiltrate
💎 Key diagnostic clue: The combination of multinucleation + nuclear molding + chromatin margination is characteristic of herpesviral cytopathic change.
•Differential diagnosis: HSV infection vs VZV infection. These cannot be reliably distinguished on H&E alone.
•Confirmation: VZV and HSV-1/2 immunohistochemistry or PCR can establish the viral type when clinically required.
#HerpesZoster #VaricellaZosterVirus #VZV #Herpesvirus #Dermatopathology #Dermpath #Histopathology #Pathology #PathologyCases