

cardiologist coronary/ peripheral intervention ❤️ imaging and physiology .🇬🇧 🇮🇹 🇧🇭 . 🐥 is a window to explore the world but never to take an action.
البحرين
Joined July 2012
- Tweets2K
- Following549
- Followers1.2K
- Likes2.7K







Pinned Tweet
Thanks for the votes
🎯 We need to clarify if Os LAD/LM are involved or not (most of the time yes)
🎯 Having multi modality imaging including CTCA and OCT helps.
🎯 Decided to nail Os but with AI using the co-registration feature


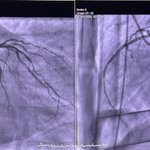
Image of the day
What is A and B space. ?
What is the pathology ?
Hint look at both frames
@DrNataliaP @mmamas1973 @mirvatalasnag @MogneeA @dukwoo_park @DFCapodanno @SripalBangalore @sbrugaletta @aayshacader @Hragy @Zill_cardio @KardiologieHH


Fawaz Bardooli, MD retweeted

📺 [REPLAY] Imaging and angiography guidance for calcified lesion PCI: when to use which device?
💡 Sharpen your strategy for calcified coronary lesions by watching the replay of this #PCRWebinar
➡️ Watch now: pcronline.com/Webinars/PCR-W…
With @Mo_A_W @FlavioRibichini @DrShereen_
#MedEd #PCI #CalcifiedLesions #OCT #IVUS #PCRWebinar #InterventionalCardiology
Fawaz Bardooli, MD retweeted

🧵 CAHP score in OHCA — why accurate data matters
1/
A new study from Qatar 🇶🇦 Heart Hospital looks at the CAHP score in OHCA.
Key message: its value depends on how accurate the data are 👇
journals.lww.com/hrtv/fullte…

Fawaz Bardooli, MD retweeted

First-in-human concept: « Access site plaque modification »
Rotational Atherectomy in the Radial Artery : ROTA-RADIAL linkedin.com/posts/claudiu-u…

Fawaz Bardooli, MD retweeted
A new study from Qatar’s HH highlights the metabolic burden in de novo HF:
• 1 in 10 newly diagnosed w DM
• 1 in 3 had unrecognized dysglycemia
• ~50% with prediabetes → DM in 26 months
@DrMarthaGulati @SJGreene_md @GULFHeartAssoc @Hragy
frontiersin.org/journals/cli…

GulfPCR 2025 in live case from Mohammed bin Khalifa centre 🇧🇭
🎯 importance of CT pre PCI planning
🎯 IVUS to guide decision in PCI
🎯 SBS LM provisional PCI
🎯 post PCI optimization guided by IVUS
@aayshacader @Hragy @mirvatalasnag @KhalidAlSaidiMD @Dr_Almubarak @DrHaithamAmin

LIVE Educational Case: Provisional left main stenting after lesion preparartion guided by IVUS
Learn from replay📺pcronline.com/Cases-resource…
Operators: @DrShereen_ @FBardooli
Procedural Analyst: @GoranEBC
Key moments
🟣33:05–43:28 : Lesion preparation - IVL
🟣51:20–54:28 : Left main - LAD stenting
🟣24:00–31:20, 43:42–50:40, 58:20–1:01:50, 1:10:27–1:17:20 : IVUS at each step
This case has been editorialised by @MartineGilard
#GulfPCR #interventionalcardiology #imagefirst #cardioed


Fawaz Bardooli, MD retweeted
LIVE Educational Case: Provisional left main stenting after lesion preparartion guided by IVUS
Learn from replay📺pcronline.com/Cases-resource…
Operators: @DrShereen_ @FBardooli
Procedural Analyst: @GoranEBC
Key moments
🟣33:05–43:28 : Lesion preparation - IVL
🟣51:20–54:28 : Left main - LAD stenting
🟣24:00–31:20, 43:42–50:40, 58:20–1:01:50, 1:10:27–1:17:20 : IVUS at each step
This case has been editorialised by @MartineGilard
#GulfPCR #interventionalcardiology #imagefirst #cardioed
Fawaz Bardooli, MD retweeted

Credits for sharing to Dr. Abdulrahman Nassiri 💐👌🤝
100 concise pearls from the 2026 AHA/ACC Guideline for Acute PE
🫀 Acute PE – 100 Pearls
1️⃣ PE risk stratification is mandatory before therapy.
2️⃣ New AHA/ACC Acute PE Clinical Categories A–E introduced.
3️⃣ Category A = incidental, asymptomatic PE.
4️⃣ Category B = symptomatic, low severity score.
5️⃣ Category C = elevated severity score ± RV strain.
6️⃣ Category D = incipient cardiopulmonary failure.
7️⃣ Category E = cardiopulmonary failure.
8️⃣ Use validated clinical probability tools.
9️⃣ Wells score remains practical.
🔟 Revised Geneva score validated.
1️⃣1️⃣ PERC rule avoids unnecessary imaging in very low-risk.
1️⃣2️⃣ Always assess pretest probability before imaging.
1️⃣3️⃣ Age-adjusted D-dimer recommended.
1️⃣4️⃣ Threshold = age ×10 μg/L (FEU).
1️⃣5️⃣ <2% failure acceptable for PE exclusion.
1️⃣6️⃣ YEARS algorithm reduces imaging burden.
1️⃣7️⃣ D-dimer strategies unsafe if already anticoagulated.
1️⃣8️⃣ Pregnancy-adapted YEARS supported.
1️⃣9️⃣ Avoid over-testing in low probability patients.
2️⃣0️⃣ CTPA is first-line imaging.
2️⃣1️⃣ Positive CTPA confirms PE.
2️⃣2️⃣ High-probability V/Q is diagnostic.
2️⃣3️⃣ Prefer CTPA over planar V/Q.
2️⃣4️⃣ V/Q SPECT better than planar V/Q.
2️⃣5️⃣ Echo cannot rule in or rule out PE.
2️⃣6️⃣ RV/LV ratio should be reported numerically.
2️⃣7️⃣ RV/LV ≥1 suggests RV strain.
2️⃣8️⃣ TAPSE <1.6 cm abnormal.
2️⃣9️⃣ McConnell’s sign indicates RV dysfunction.
3️⃣0️⃣ Report chronic thromboembolic signs on CT.
3️⃣1️⃣ LMWH preferred over UFH initially.
3️⃣2️⃣ DOACs preferred over VKAs.
3️⃣3️⃣ DOACs reduce major bleeding.
3️⃣4️⃣ Extended anticoagulation if unprovoked PE.
3️⃣5️⃣ Treat first episode ≥3–6 months minimum.
3️⃣6️⃣ Persistent risk → continue beyond 6 months.
3️⃣7️⃣ Evaluate bleeding risk regularly.
3️⃣8️⃣ IVC filters not routine.
3️⃣9️⃣ Use IVC filter only if anticoagulation contraindicated.
4️⃣0️⃣ Remove IVC filter when safe.
4️⃣1️⃣ Category A patients can be discharged.
4️⃣2️⃣ Category B often early discharge.
4️⃣3️⃣ Category C requires hospitalization.
4️⃣4️⃣ Category D needs close monitoring.
4️⃣5️⃣ Category E needs aggressive intervention.
4️⃣6️⃣ Persistent hypotension defines high risk.
4️⃣7️⃣ Use biomarkers for risk stratification.
4️⃣8️⃣ Troponin elevation signals myocardial injury.
4️⃣9️⃣ BNP elevation suggests RV strain.
5️⃣0️⃣ PE Response Teams (PERT) recommended.
5️⃣1️⃣ Systemic thrombolysis for high-risk PE.
5️⃣2️⃣ Consider advanced therapy in D1–D2.
5️⃣3️⃣ Catheter-directed thrombolysis reasonable.
5️⃣4️⃣ Mechanical thrombectomy evolving option.
5️⃣5️⃣ Surgical embolectomy when indicated.
5️⃣6️⃣ ECMO for refractory shock.
5️⃣7️⃣ Avoid routine thrombolysis in low-risk PE.
5️⃣8️⃣ Evaluate for contraindications before lytics.
5️⃣9️⃣ Monitor for intracranial hemorrhage risk.
6️⃣0️⃣ Early recognition saves mortality.
6️⃣1️⃣ Assess hemodynamics continuously.
6️⃣2️⃣ Monitor oxygenation closely.
6️⃣3️⃣ HFNC or NIV may be required.
6️⃣4️⃣ Mechanical ventilation cautiously.
6️⃣5️⃣ Avoid aggressive fluid overload.
6️⃣6️⃣ Use vasopressors if hypotension.
6️⃣7️⃣ Norepinephrine preferred.
6️⃣8️⃣ Reassess category over time.
6️⃣9️⃣ Clinical status can evolve rapidly.
7️⃣0️⃣ Repeat imaging only if clinically indicated.
7️⃣1️⃣ Ask about dyspnea at every follow-up visit.
7️⃣2️⃣ Screen for CTEPD at least 1 year.
7️⃣3️⃣ Persistent symptoms need evaluation.
7️⃣4️⃣ Chronic RV strain needs specialist input.
7️⃣5️⃣ Exercise intolerance must be addressed.
7️⃣6️⃣ Educate patients about recurrence risk.
7️⃣7️⃣ Travel guidance important.
7️⃣8️⃣ Activity resumption individualized.
7️⃣9️⃣ Avoid routine thrombophilia testing acutely.
8️⃣0️⃣ APS alters anticoagulation choice.
8️⃣1️⃣ Cancer-associated PE requires special planning.
8️⃣2️⃣ Pregnancy PE requires low-dose protocols.
8️⃣3️⃣ Avoid over-radiation in pregnancy.
8️⃣4️⃣ Avoid under-treatment of high-risk PE.
8️⃣5️⃣ Document RV strain in report.
8️⃣6️⃣ Quantify clot burden cautiously.
8️⃣7️⃣ Clot burden alone not treatment determinant.
8️⃣8️⃣ Clinical severity score essential.
8️⃣9️⃣ Hemodynamics trump imaging.
9️⃣0️⃣ Biomarkers add prognostic

Fawaz Bardooli, MD retweeted
Complex multivessel disease: CT- and IVUS-guided complex bifurcation PCI - #EuroPCR LIVE educational case
📺pcronline.com/Cases-resource… (via your free My PCR account)
Opearators: @NievesGonzalo1, @JEscaned
Procedural analyst: @FBardooli
Watch this replay, chapterised by @MartineGilard, to optimise your learning experience:
Key moments
🟣17:50-19:40 - Cx bifurcation PCI with provisional stenting
🟣20:40-24:13 - CT analysis
🟣26:03-44:44 - CT/angio co-registration
🟣1:02:57-1:08:39 - Dual microcatheter liner for diagonal wiring after LAD stenting
🟣1:17:53-1:20:31 - Post-procedural analysis
#interventionalcardiology #CardioEd


70 years active lady
AWMI last month PPCI to LAD.
disease RCA.
What would you do to RCA. Pt is Asymptomatic
@shoaib9702 @mmamas1973 @PCRonline @mirvatalasnag @ANazmiCalik @CuissetDr
@Hragy @RHAAttar @w_jyg @KardiologieHH @Zill_cardio
@adil_jabri @yaqoub_lina @Zayer_h


I completely understand PCI supporter✅
Imagine this lady come to visit me 2 months back with angina pain, I fix her LAD as it is tighter and correspond to RWMA on Echo, then I have the RCA as it is 👆. Stable angina symptoms medical VS PCI using contemporary data @BaoGTran.
Thanks all for your thoughts
Here what happens in reality.
Pt reviewed n clinic - Asymptomatic booked her for DOB stress echo(-ve for ischemia)
Comes to clinic again this time ME, “Can’t be“ possible FN results.
I book for angioplasty RCA guided Physiology 👇😳 these results


Fawaz Bardooli, MD retweeted

COMPLETE & Co. ≠ automatic PCI
I generally agree with complete revascularization when indicated.
In a stable, asymptomatic patient:
GDMT → functional assessment → PCI if ischemia.
Evidence ≠ mandate for ad-hoc non-culprit PCI.
Fawaz Bardooli, MD retweeted

Wonderful ongoing collaboration between @GULFHeartAssoc @SCAI in the 3rd annual @GHASCAISHOCK conference in Kuwait. Joined by the Sheikh of PV Loops @BurkhoffMd, Sheikh of Lava ECMO @PedroMDMSc and wonderful friends & hosts @FBardooli @rashaalbawardy @abdarabi @falkindi404


Fawaz Bardooli, MD retweeted
🎆#HappyNewYear2026, dear #CardioX🫀
As we enter 2026, I would like to sincerely thank you
for the tremendous #support+#collaboration throughout 2025
Special thanks for our shared commitment to education, training, and innovation in interventional cardiology.
🙏 A special thank you to Prof. Dr. Alexander Ghanem, who enabled me during my four years as an elected AGIK nucleus member to develop and implement innovative educational formats, including:
• the #AGIKSimulationCourses (in collaboration with @Mentice)
• the #AGIKSimuClass at DGKHeartDays (in collaboration with #SIMULANDS)
• strengthened international networking, and
• the strategic development and international positioning of the AGIK Interventionsakademie in close cooperation with PCR and #EAPCI.
🙏 My sincere thanks also go to @alaide_chief/@EAPCIPresident for driving the #EAPCI education initiatives forward:
With the establishment of #EAPCIEducationalPathway with #OnsiteCourses (coronary & structural) and the #OnlineModules currently in production, which will comprehensively reflect the #EAPCICoreCurriculum, structured and sustainable education is reaching a new level.
We created sustainable webinars and #EAPCIJournalClubs for the global community: #MoreToCome
🙏 I would also like to thank the #ACVC team — Prof. Ingo Ahrens (@ACVCPresident), Dr. Jordi Bañeras and Prof. Alessandro Sionis — for the successful establishment of the #ACVC/#EAPCI #CardiogenicShockSchool, a key educational pillar in one of the most challenging areas of our field.
🚀 2026 is ahead with exciting new projects, most notably the
👉 #EAPCISummit26, February 19–20, 2026, in Munich.
I am very much looking forward to welcoming many international colleagues and, as Track Coordinator, to delivering more than 10 hands-on workshops together with @marioiancardio — covering topics such as
Bifurcation PCI, Transseptal Puncture, Calcium Modification, M-TEER, and more.
🔵 Education. Collaboration. Innovation.
🔵 See you in Munich!
🙏 My sincere thanks also go to everyone I cannot mention individually — my team at Schön Klinik Hamburg Eilbek, the teams at @escardio and @DGK_org, and the many friends and colleagues who accompanied and supported me throughout 2025: #YouAreAmazing!
I wish all of you a happy, healthy, and successful #2026 — both professionally and personally.
#HappyNewYear2026 #CardiologyCommunity #InterventionalCardiology #EducationMatters #EAPCI #SimulationBasedTraining #EAPCISummit2026 #SeeYouInMunichIn2026

Young man has lost two of his brother with SCD!
Q: where is LAD
Q: any PCI?
@mmamas1973 @mirvatalasnag @ANazmiCalik @CuissetDr @nicolasdumonte1
@Hragy @rashaalbawardy @RHAAttar @w_jyg @KardiologieHH @Zill_cardio
@A_Esmaiel85
@Alshehri_MD
@aayshacader
@PCRonline
Pleasure to be within this Team
Special thanks to our amazing Social Media Team for helping make #GulfPCR 2025 shine✨!
They were so busy contributing to the Course that catching them all in one photo was mission impossible 😉
@FBardooli @Hragy @DrAlsubei @johaniMD @fjsawaya


Day 2
#GulfPCR
Discussion takes place beautifully in case corner with coronary structural complicated cases. The beauty it is international
@Loaiabudaqa @PCRonline
@shoaib9702 @ANazmiCalik @CuissetDr @nicolasdumonte1
@Hragy @rashaalbawardy @RHAAttar @KardiologieHH @Zill_cardio

Day 2️⃣ #GulfPCR @PCRonline
High risk TAVI ( valve anatomy and patient profile )
From National guard Jedah @AlkashkariWail @rashaalbawardy @DrAlsaiediAB
Come to see how challenges are tackled
@shoaib9702 @ANazmiCalik @CuissetDr @nicolasdumonte1
@Hragy @w_jyg @KardiologieHH


Will done team @rashaalbawardy @DrAlsaiediAB
Enjoyed the case
Learned the importance of anticipation of problems is as good as treating them.